AI-assisted translation
This version was translated from Italian by Complexe Systémique with the help of artificial intelligence. In case of doubt, the original version prevails.
Connessioni · Gender identity
Gender representations
When a child discloses gender dysphoria, the whole family enters a transition, on timescales that do not match. Drawing on their work with one family, Federico Sandri, Roberta Marchiori and Tommaso Bonavigo propose enriching the genogram with three-level symbols, genetic, psychological and bodily, built with the person and their relatives to give the family a shared language.
Unofficial English translation. This article is a translation of Rappresentazioni di genere, by Federico Sandri, Roberta Marchiori and Tommaso Bonavigo, published in Connessioni (Centro Milanese di Terapia della Famiglia), new series, no. 1 (2017), under a CC BY 4.0 licence. Translated by Complexe Systémique in November 2026 with the help of artificial intelligence: the original Italian text has been translated into English and reformatted, which constitutes a modification of the work under the terms of the licence. The paragraphs and headings are those of the journal; the biographical notes that open the page are included in the presentation of the authors, without e-mail addresses; the epigraph from Gianrico Carofiglio is given in indirect speech; quotations are translated from the Italian, except Avery Jackson’s words, given as published in English by National Geographic; titles of works are given as the article cites them; the two figures are reproduced with translated captions; a few typographical errors in proper names (Boszormenyi-Nagy, Mascellani) have been silently corrected. This translation was made neither by the authors nor by the journal, who are not responsible for its content or for any errors. The original version prevails.
It is not only the physical body and form of the transgender person that goes through a transition […]; it is the body of the whole system that has to go through a process of loss and reaggregation, of revisions and reformulations.
Federico Sandri, Roberta Marchiori, Tommaso Bonavigo
As an epigraph, Gianrico Carofiglio (“Thaiti,” in Passeggeri notturni) recalls the need to rectify names: when names no longer correspond to reality, language loses its object, action becomes impossible and human affairs lose their meaning; the true task of those who govern is therefore to rectify names.
Introduction
As the literature emphasises, gender dysphoria – defined as a marked incongruence between experienced/expressed gender and assigned gender (APA, 2014) – is almost always associated with great psychological suffering, which may show itself as anxiety, depression or relational difficulties, up to suicidal ideation. These symptoms are closely linked to the difficulties that the family and the social system have in accepting this expression of identity (Rigobello, Gamba, 2016). Research by the leading scholars in the field indicates that the psychopathological risk is not linked specifically to gender incongruence itself, but rather to the traumas these boys and girls suffer in the family, at school and in their other living environments, because what they feel to be their psychological and sexual identity is not recognised (Lingiardi, Giovanardi, 2017). This state of non-acceptance by the community persists into adulthood and is amplified, as we know, by cultural stereotypes.
Over years of clinical work supporting research at the Psychiatric Clinic of Trieste, and of support for local and cultural organisations working with minorities at risk of social exclusion1, the systemic approach has made it possible to broaden our perception of the family’s involvement in the dynamics of the path that leads to Sex Reassignment Surgery (SRS). In counselling, it has always seemed appropriate to analyse, and to direct the work towards, the whole system in which the transsexual person lives and expresses themselves, not only to try to protect the expression of their change, but also to give meaning to the doubts, the reflections and the ways of understanding transsexuality throughout the system.
The intertwining of this specific work experience (Sandri, 2013, 2015, 2016) with experience of working with different family compositions from a systemic standpoint (Marchiori, 2012, 2013, 2015, 2016) led us to reflect on the use of conversational techniques and clinical tools typical of the relational model, such as the three-generation genogram, in cases where these complex transitions are being faced.
As Marchiori and Viaro (2015) noted, the way quantitative, qualitative and narrative data are collected and represented graphically will influence the decisions and actions that follow; precisely because it requires data to be selected and reorganised, the genogram is in itself an operation of restructuring, tied both to theoretical premises and to clinical needs.
Some proposals and reflections presented in the study by Sandri, Bonavigo and Marchiori (2016) on the graphic representation of transgender people form the starting point, together with the analysis of a case, for further considerations on working with families in which the many-sided issue of gender identity emerges.
Clinical case: part one
The Vanzi family was referred to Dr Sandri by a colleague for family work. The household consists of the mother, Donatella, 46, a post office employee; the father, Manlio, 45, a member of the Guardia di Finanza; the son, Luigi, 19, a mechanical engineering student in Trieste; and Luisa, 17, in her fourth year at a language-focused secondary school in Padua.
In the first session, while data and information are being gathered on three generations of the family and on the social context, obvious conflicts emerge between mother and daughter. In particular, the attitude (as the mother describes it) of “restlessness and defeatism” with which Luisa approaches school and life seems to serve to bring to light a distress that will become more and more explicit over the following sessions.
Luisa has had a girlfriend her own age (Maria) for more than a year; this relationship leaves the mother “puzzled and a little worried,” both because of her daughter’s choice and because she wonders “what will happen when the relatives find out.” Manlio seems more involved in supporting Luisa than the mother, whom he considers “overly anxious about normal moments in a teenager’s life”; the father tries to understand the reasons that lead his daughter to feel, as he puts it, “restless and disoriented.” The brother seems to be listening to what is happening in the system rather than reacting by defining solutions or alternative patterns of relating.
In the second session a crucial piece of information emerges, bringing new elements into the family relationship. Luisa says she feels “unhappy because I am a man trapped in a woman’s body” and that for a year now she has been called Cristian in her most important friendships and in her relationship with her partner. This statement startles the mother, and the father asks the therapist for clarification to make sure of what his daughter has just said; Luigi falls silent. The session ends with the family dumbfounded, while the therapist reassures them that time will be set aside in the next session to understand better what has been said.
In the third session, after some reflections are offered on the effects of their daughter’s declaration, the mother and father appear bewildered and still disoriented, above all because Luisa/Cristian seems resolute and convinced of what she has said; the parents feel they are “living on a different timescale from their daughter, who is already so determined.” Luigi bursts out, in tears: “Stay as you are!”; at the end of the session the mother says: “I feel I have lived with someone I don’t know, an intruder in disguise.”
Given the heavy emotional load, it seems useful to let some of the emerging feelings settle, to be taken up again later, and attention shifts to other themes. After explaining the difference between gender identity and sexual orientation, and trying to help the family clarify its various questions, the therapist announces that work on family relationships will resume at the next meeting.
New families and families as they have always been
In the contemporary Western landscape, what has perhaps always happened in less heteronormative and less gender-normative contexts is becoming ever more evident: the family shows itself to be anything but a device defined by “natural” laws. “There is nothing less natural than the family,” writes Saraceno (2012); this does not mean it is unnatural, but that the family is a social, legal and normative construction which – as Durkheim (1999) would say – has gone from social construct to “social fact,” taken for granted both as an organisational model for society and as a mental map guiding subjective choices.
As a social fact, the family is a cisgender, heterosexual unit formed by a two-parent union; yet if we look at the family from an anthropological and historical point of view, we find that the way this normative process has taken place has varied greatly across time and space. One speaks of kaleidoscope families, defined also subjectively in terms of boundaries and belonging: some people count one grandmother as part of the family but not the other, some their father’s partner, some their nanny; in this reading, dominant value is given to the colour of affections rather than to genealogy. “New families are the families of always” insofar as now, at this historical moment, they have found a way of defining themselves that takes them out of the shadow of an imposed normativity; they have found names to define themselves and distinguishing features that do not refer back to dichotomous paradigms, but they are families that have always had their own emotional dignity, even if they were not represented as such socially2.
“Rainbow families” (Ferrari, 2015) is one possible definition of a system in which one or both members of the couple are homosexual; yet this is only a name that conveys a feature of the parents’ sexual orientation, and says nothing about the orientations of the others, about gender identities, or about how the family system is made up. What is missing are ways of communicating a complexity, and the different strategies for negotiating and working through it, in a context where the words to express it are (still) lacking.
Reflections and extensions
To represent the world, we all need concepts, categories and schemas that can be at least partly shared. Gender acts as a minimal, embodied and monadic variable, almost never subjected to critique, and offers itself as an automatic category for classifying people (Graglia, 2012). Family relationships emerge as constitutions arising from the pooling of meanings born of the interaction of individuals who take an active part in a collective narrative, made up of an intrapsychic level and an interpsychic, relational level, and of their blendings. Over time, meanings have contributed to the construction of a living matrix that remaps itself through communication circuits giving definition and consistency to the events in which the members take part. Patterns stabilised over three generations build family mythologies, as Boszormenyi-Nagy (2014) suggests. In any relationship – Andolfi and Angelo (1987) write – a myth is created, and the information gaps in the process of building the bond and mutual knowledge are filled through the formation of stereotypes.
As Butler (2005) suggests, gender, in its psychic value, is a myth that is certainly very stable and statistically less discussed than others; since the child wants to go on living, both psychically and socially, there is no way for the child to emerge outside the attachment and the myth that gave belonging and love. Like all systems, the family tends towards conservation, stability and homeostasis (Jackson, 1967); this state of equilibrium, which transcends the individual, allows the system to infer a linear kind of logic and to maintain expectations.
No one expects such an unexpected and statistically infrequent event as Gender Dysphoria (GD) to occur: the system reacts to it with emotional and behavioural discordances, often linked to unresolved issues. As Andolfi and Mascellani (2010) already pointed out for families of children with DSD (Disorders of Sex Development), we believe that narrating the system’s experiences is essential in offering families support with the feelings of inadequacy, guilt and marginalisation they frequently experience.
Families need support to tolerate uncertainty and anxiety about the development of identity (Monceri, 2015). Research by McCubbin and Patterson (1983) showed that, in equally stressful and critical situations, families that had carried out a shared reconstruction of the meaning of the problem had managed to rebalance their system in a positive direction. According to Olson’s hypothesis (1990), the more an individual or a family, in times of stress, favours emotional closeness and flexibility towards rules and power structures, and develops good communication, the better the chance of overcoming the stressful event (Mariotti 2002).
The alteration of the gender parameter, in itself considered immutable, forces the parents of the transgender person to question the mental representations of their children they have internalised (Massara et al., 2012). Many patterns of family interaction are thrown into crisis: family members often say they feel betrayed by incorrect or falsified communication3; they question past conversations and the good faith of the member who is renegotiating the rules of interaction and who has behaved, as the patient’s mother put it, like “an intruder in disguise”; they feel emotionally distant because they are hurt, and find it hard to empathise with the experience of the dysphoric person (Lev, 2013). As Massara et al. (2012) suggest regarding DSD cases, the system finds itself having to bear a high level of “indeterminacy”; the alteration of gender can be more destabilising than a psychopathology or another critical event, because it asks the members of the system to reorient themselves very quickly, and people are often unable to respond adequately.
With some adverse events, the system reorganises itself in search of shared, discussed and negotiated solutions; with the “GD” event, the solutions the system first puts forward are in most cases attempts at normalisation (Rigobello et al., 2016) and a return to the ranks of biological gender (as in the case cited, where the brother says “stay as you are!”, which is not in fact an acceptable proposal for the individual and is therefore rejected, often exacerbating conflict and misunderstanding).
The system does not yet have an alphabet for understanding what is happening and has already happened. As Watzlawick (1971) pointed out, a phenomenon remains unexplainable as long as the range of observation is not wide enough to include the context in which it occurs. By failing to consider the relationship between the event and the matrix in which it takes place, between an organism and its environment, the observer will be faced with something “mysterious,” baffling, or will end up attributing to the event properties it may not have (Watzlawick et al., 1971). The family remains suspended in the inexplicability of an event that phenotypically “makes no sense” to some members, yet for one of them has a reality value that allows no discussion or criticism, and grants no time.
According to Claudia Hammond (2013), the experience of time is actively created by each person’s mind: emotions, concentration on a more or less pleasant activity, age, expectations and many other factors help produce a subjective perception of time.
The variable “time” runs on two separate tracks: the person with GD, having declared what had always been kept silent, asks for and demands immediate recognition, in the present, with a force that almost has the flavour of compensation for the time spent hiding what was already emotionally evident. The other family members, in their bewilderment, need time to become aware of what has emerged: it is a mediated, reasoned time, never really finished, that gets lost searching for the clues of a hint, of an expression in which that secret could have been caught, the secret that in the present space makes everything unreal. The parents call to mind the time of the birth and the early experiences of growing up, mentally checking the existence of a newborn body, then a child’s, a teenager’s and an adult’s, that has always been the same, consistent with and corresponding to their reading of biological gender.
André Green (1983) hypothesises that the first of the organisers of sexual identity is the parents’ early and unconscious attribution of a sex to the child; after birth, according to Infant Research, there are unconscious labels that convey, very subtly, in every interaction, the father’s and mother’s feelings about the child’s femininity or masculinity. The work of Mahler et al. (1975) on how, through physical contact with the mother, little boys and little girls come to perceive themselves as beings endowed with a sexed body highlighted the importance that the perception of one’s bodily Self takes on in acquiring a sense of identity. It should not be forgotten, however, that while the child is building a gender identity, the mother and father assume that it can be equated with the child’s biological gender: for them it is a completely overlapping, settled fact that statistically raises no questions.
While the parent is willing to believe that the child may have tastes different from their own in food, drink and colours, and even considers this an important value for growth and individuation, the parent is almost always unaware that there may be an experience of incongruence between the sex at birth and the psychological and behavioural expressions of gender identity (and, once this is revealed, often regards it as a disvalue rather than as a conceivable variance). Once labelling has been negotiated and accepted by the family, all behaviour takes place by virtue of that label (Fruggeri, 2015).
When a system is sufficiently able to readapt and to find room after an initial disorientation, it may happen that it welcomes the relative’s GD in a dichotomous way: in some cases, even defensively, families seem to propose a male/female option that nonetheless sounds like an injunction.
As Nestle et al. (2002) and Malpas (2011) suggest, one of the main goals, not only with transsexual patients but above all with families, is to shift, cognitively as well, the view of gender from an either/or position towards a both/and one4; from a classificatory approach towards more flexible positions. Di Ceglie (2014) states that often – in keeping with the changing times and with ever more nuanced definitions of gender, as also enshrined in DSM-5 (APA, 2014) – many patients ask therapists and families, more or less explicitly, to overcome the constraints of gender stereotypes and to help them find new positions and combinations (Factor et al. 2008; Alegria, 2016).
Genogram and gender identity
The genogram is a tool that sets out to read gender identity as a single, significant variable described in polar terms; when the tool was theoretically defined, two genders were referred to: male and female (McGoldrick et al., 1985). New codings were later proposed for sexual orientation (Hof, Berman, 1996), and today some revisions also make room for gender identities (Belous et al., 2012) and for new emerging non-conventional identities (McGoldrick et al., 1985). We have already observed that the genogram is not a normative tool, but defines a representation that needs to be broadened by the narratives of the system taking part in compiling it (Sorrentino, 2008; Cirillo, 2011): as Bowen (1980) and others (Jolly et al., 1980; Hardy et al., 1995; Lupoi et al., 2002) noted, the therapeutic purpose of the tool lies precisely in the joint co-construction between system, individual and therapist. It is this substantial element that allows the tool to become a space for reasoning that is neither right nor wrong, but seeks to propose, and thus to broaden, the space of possible realities for the system, all the more so when it is used as a clinical tool.
From our review of the literature we identified a limitation in the use of genogram symbols in non-conventional situations (Sandri et al. 2016): the experience of transsexuality is not taken into account in its complexity. A model that considers only biological variables cannot be sufficiently comprehensive and informative about the identity construction one wishes to represent in these cases. The subject’s gender is expressed, as we have seen, in a variable weighed down by layers of meaning about being male or female (Poggio, 2004), or about no longer wishing to be either (in some gender organisations), and we think it important to take this into account in the graphic representation. Identity construction takes shape in a past, a present and a future, and needs the description of at least three levels of experience (psychological, bodily, genetic) to be analysed, and, to be truly informative, a level of systemic sharing.
We therefore propose, clinically, to build with the person concerned and their family a representation of the self that best expresses how the person feels, who they are and who they want to be, as for example in the following representations.
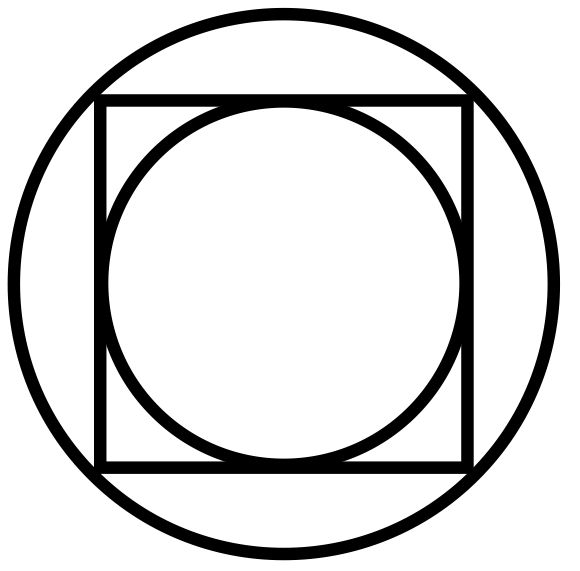
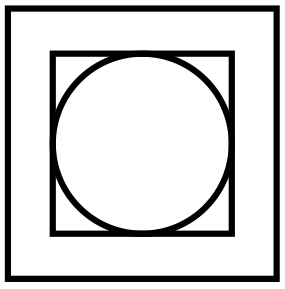
We have noticed (Sandri et al. 2016) that by widening, as in the figures shown, the possibilities of self-representation, people not only feel better understood and respected but also reflect more precisely on how they feel physically and psychologically, both individually and together with their family. In these representations, as specified, we started from the genetic level, but in others it may be useful to begin with emotional experience. As reported in the issue of National Geographic (January 2017) devoted to the “Gender Revolution,” many people feel that they have become who they were and who they were meant to be; Avery Jackson, a nine-year-old transgender girl, says: “The best thing about being a girl is, now I don’t have to pretend to be a boy” (p. 3).
As Di Salvo (2011) describes, in the field of transsexuality – not only therapists, but the very family in which a member presents GD – rely on scripts and stereotypes, using them as efficient heuristics6 to save time and mental processing. These strategies are meant to reduce cognitive dissonance in the face of irreconcilable ideas. It is necessary to widen the aperture of alternatives so as to bridge the gap between how things should be and how they actually are (Cecchin et al., 1997); this is what truly allows a qualitative theory to be built.
We believe that, in order to render more fully the possible scenarios in gender variance without overlooking the emotional events expressed throughout the system, it is necessary to define a version of the genogram that takes time into account – made explicit as the person’s history and psychological and physical development within the system that saw the person manifest GD – and that serves as a shared reading tool for the whole family.
Clinical case: part two
As the therapy continued, after some theoretical explanations aimed at establishing a semantic frame everyone could understand (the differences between sexual orientation, gender identity, biological sex, gender role and perceived gender), it was suggested that the genogram be used to make explicit, graphically and in a shared way, some of the critical elements that had emerged earlier. Work therefore resumed, giving shape and value to the emotional and psychological movements connected with the phenomenon of transition affecting the system.
To give this process more structure, we decided to report sequentially the most salient themes that emerged during the sessions and the reflections connected with them.
It is clear to all members of the system that Luisa/Cristian cannot and does not want to go on being represented as female, so possible graphic representations are proposed, along the lines described in the reflections set out above.
Luisa/Cristian graphically expresses the three levels, genetic, psychological and bodily. This representation (which in fact gives visibility and dignity to the different areas in which GD is embodied) prompts many reflections in the system: Luisa/Cristian feels better represented and says he feels calmer “…also because I feel that what I couldn’t get my folks (parents) to understand with words is now clearer.” The family members welcome, with many questions, the introduction of the graphic representation built by Luisa/Cristian: to them too, “what was described before is clearer”; “I feel less confused now,” says the mother, while stressing the need for time to reflect on and work through what has emerged. The father still shows some unease, but seems more open and receptive than in previous meetings.
Through the graphic sign, a system of meanings seems to have become more shareable; although it remains partly bound to the individual’s own value, it can now, like the underlying emotional content, at least be discussed and negotiated: it is not possible to coordinate or to define a common goal without, as the constructionist approach suggests, a shared repertoire (Leone, et al. 2013).
Giving a graphic sign to the family’s experience was a way of enriching its system of meanings without devaluing what each member was going through. Representing the effect of transition on the person made access to mentalisation and change easier.
In later sessions, we considered what would happen if the hormonal pathway were undertaken, which would bring significant changes to Luisa/Cristian’s body. The graphic representation helps the system become aware of the future projection and, at the same time, introduces the idea that while something changes phenotypically, something else remains constant. The patient himself needs to understand that, although morphology changes, some psychological and biological elements do not, even with surgery. Paying attention to bodily and psychological transition helps clarify the process in which the system is immersed, as Menvielle (2012) also suggests.
The parents ask for information about the parameters of a path, a process of change unknown to them, concerning both its bodily effects and the psycho-emotional health of their son and of themselves. As Budge et al. (2013) emphasise, offering the person directly concerned, the parents and the wider system of belonging precise information on gender identity issues, not only in medical terms but also in psychological and emotional ones, reduces suicide risk among LGBT adolescents, fosters their inclusion in the social community and their emancipation from the family system, and helps them understand the process of “transition.”
Family members, as Rigobello et al. (2016) explain, bring an atypical request aimed at normalising a third party, the child, who instead, through their distress, breaks the family homeostasis by asking the parent, often indirectly, to find on their behalf the best strategy for managing that distress. On the one hand the parent wants to support and help the child; on the other, the parent comes up against their own set of values, fears and insecurities about the path the child will have to face, and the fear that even once the goal is reached the child will not be satisfied with the outcome7.
It is not only the physical body and form of the transgender person that goes through a transition (Ferrari 2007), first imagined and then realised; it is the body of the whole system that has to go through a process of loss and reaggregation, of revisions and reformulations.
The therapeutic process can be conceived as a work of narration repeated over the timescales of the various agents in the system; its aim is to build, together with the whole family, awareness of its own life course within a temporal sequence in which the various elements at play reconnect, drawing on past assumptions to project towards the future (Dallos, 1997). As the patient’s mother recalls, there is a feeling of “living on different timescales.” The time of the story being told moves back and forth for the system: “what will happen first, and what will happen after,” “tell me again: but then what will happen,” “I need to ask again” are questions in which this theme becomes clearly explicit, and which reflect on the one hand the need to re-narrate information, and on the other the need to let the feelings activated by family and therapeutic communication settle.
Finally, it seems particularly useful to reflect on what will happen in the wider context of belonging when the child’s change becomes more explicit or takes place phenotypically. One of the concerns that emerges in clinical work is having to explain the child’s change to relatives and friends: being able to analyse, even imaginatively, what may happen in the reality of relationships fosters the emergence of strategies and skills that the family and its members did not think they had, and at the same time can foster the perception of a cohesive systemic unity working towards a shared communication of the event. It is very important, as the work with families of adolescents with GD published by Petiva and Spirito (2015) shows, to help the family “work as a team” by sharing a common language within the family, which helps it reorganise towards the wider social context and avoid social self-exclusion.
Conclusions
A family in which a child presents GD needs to recode the meanings of an experience that, in most cases, could not have been imagined, and which, when it comes to light, causes major upheaval for all its members.
The clinician’s task is to offer spaces in which non-conventional identities and the systems in transition8 themselves can reach a first agreement on terms, a ground for a possible and communicable representation. Working with the family and using the genogram, with the care suggested here, is a way of shedding light on a story that needs to be seen in order to take the form of a narrative representation (Poggio, Jedlowski, 2004).
The studies we were able to consider analyse at length the effects of GD on the transsexual person: they examine the situation in childhood and adolescence, assess its emotional and social repercussions, and analyse the effect of stigma for the child and for the adult; yet it remains important to stress further the impact of GD on the family system and the modulation of relational dynamics over time. The whole system involved needs to find a space in which to give meaning to the situation, to face the upheavals under way and the new needs emerging (Lev, 2013), to mature, and to build a wider and more welcoming emotional frame. From this perspective, taking on the main system of belonging and using methods common in systemic practice, adapted to this clinical specificity, can help to:
- bring out the different points of view and the “unsaid,” making room for the experiences of all members of the system;
- give GD a new form, defining it with graphic signs that resignify and broaden the family’s cognitive and emotional experience;
- make the ongoing process visible in relation to the time variable;
- build shared ground for communication within the system;
- help the family reorganise in relation to the wider social system.
Complexe Systémique: key points
The article dates from 2017 and shows it: the vocabulary (“transsexuality,” “GD person,” “FtoM”) has since moved on, and the case, sketched in broad strokes, illustrates more than it demonstrates. Its contribution to family practice remains clear. It shifts the question from the individual to the system: the whole family is “in transition,” on diverging timescales, with the urgency of recognition on one side and the need to reread the past on the other. It also offers a simple tool: a three-level genogram symbol, genetic, psychological and bodily, built with the person and their relatives, which helps distinguish what changes from what stays the same and opens the conversation rather than settling it. Worth retaining are the attention paid to normalising responses (“stay as you are!”), the place given to information about gender identity, and the idea of helping the family “work as a team” in facing the people around it. The genogram becomes a co-construction again, not a mere record. Read alongside the essentials on the genogram, and a study of trans children and their parents navigating transition.
Notes from the original
1 This refers to associations such as Arcigay and MIT, for which consultancy, support and training were provided. In particular, with regard to Gender Dysphoria, Dr Sandri initiated the “Transizioni Attive” (Active Transitions) project, aimed at supporting people in transition, couples and families through the complex pre- and post-operative process. This work has been carried out since 2011 at the Urology Clinic and the Plastic Surgery unit of Cattinara Hospital in Trieste.
2 Think, for example, of families after the Second World War, in which the absence of a spouse, a child or a blood relative allowed households to re-form along different lines, according to economic needs, emotional belonging and empathy in suffering. In Friuli after the earthquake, for example, many family systems re-formed according to where people lived and to the tragic and unexpected loss of some relatives (in some cases of entire families); the idea of an identity to be rebuilt from the rubble of a story now over made it possible to build recomposed, plurinuclear, non-heteronormative family systems. As Fruggeri (2001) suggests, any “diversity” is justified by the shared social context in which the family is set. Today, in Italy, the heterogeneity of family forms is no longer an “exotic” phenomenon to be viewed from afar. The Italian social context is now woven through with stepfamilies, single-parent families, same-sex couples claiming the right to social recognition, families of different or mixed ethnic backgrounds, and also a growing number of families with non-biological children, or nuclear families that less and less follow the most deep-rooted traditional models.
3 As Turnaturi suggests, jealously guarding a secret without sharing it with those close to us can be regarded as a betrayal. What the family experiences is the realisation of a fact that, in the mind of the person with GD, already has a level of definition that makes it a given reality and that, as such, demands to be seen and acknowledged; in the system’s perception, the fact is not yet a real event, but a variable that is called into question, about which doubts and questions arise, and which one tries to negotiate, partly to safeguard the previous image.
4 This refers to a set of English words that can also function as conjunctions. Either/or refers to a confrontation between two antithetical positions that tend to cancel each other out – in Italian one would say aut/aut; the form both/and, by contrast, emphasises the possibility that two terms, despite a possible dichotomy, may be read as part of a relationship that does not negate but contemplates several possibilities. With regard to gender, the point is thus the shift from a view that negates what stands in antithesis to one that aims instead at integration.
5 The symbol in Figure 1 sets out the three levels of experience of a FtoM (Female to Male: a person biologically female who wishes to transition into a male body) transsexual person; from the innermost to the outermost, one can read the genetic level (female), the psychological and emotional experience (male) and the current bodily appearance (female). Figure 2 shows the symbol describing the outcome of the transition process: the genetic level (inner circle) and the psychological and emotional experience (middle square) remain unchanged, while the bodily appearance that the person wishes to show and attain changes, in some cases also through hormone therapy and SRS surgery.
6 In psychology, heuristics are simple and efficient rules proposed to explain how people solve problems, make judgements and take decisions when faced with complex problems or incomplete information. The principle justifying the existence of heuristics is that the human cognitive system is a system with limited resources which, being unable to solve problems through algorithmic processes, uses heuristics as efficient strategies to simplify decisions and problems. Although heuristics work well in most everyday circumstances, in some cases they can lead to naive errors.
7 As in Di Ceglie’s metaphor, which cites Ulysses’ voyage between Scylla and Charybdis as a turning point and a choice between one of the two poles of conflict. The event of transsexuality forces the system, and particularly the parents, to choose between allowing a (plausible, imperfect, partial) modification of the body for the sake of a (plausible, imperfect and partial) improvement in psychological well-being, and opposing bodily change in the name of an imagined biological supremacy that aims to preserve what is there at the expense of a mind embodied in an imperfect physicality, perhaps never truly bearable. And the reality is that in the end the parent has to accept the frustration of not having the power to oppose what the child wants. The temptation to fall into a purely biological reading that intervenes on the body, or a purely psychological one that underestimates the distress of a body the person does not feel to be their own, must be faced with constant caution, in awareness of a room for manoeuvre that is always very limited.
8 We find it useful to use the term “system in transition” because we think it important to weaken the idea that the person with GD undertakes the transition path alone, whereas in our experience the whole family enters this process. We are convinced that the whole family goes through a significant change that needs to find a sense and a new meaning, and the psychological support the person with GD requests (often informative and clarifying) often differs, both in manner and in timing, from that requested by the family.
References
AA.VV. (2017), Gender la rivoluzione, National Geographic, 39 (1): 3.
American Psychiatric Association (2014), DSM-5: Manuale diagnostico e statistico dei disturbi mentali, Raffaello Cortina, Milano.
Andolfi, M., Angelo C. (1987), Tempo e mito nella psicologia Familiare, Bollati Boringhieri, Torino.
Andolfi, M., Mascellani, A. (2010), Storie di adolescenza, Raffaello Cortina, Milano.
Alegría, C. A. (2016), “Gender Nonconforming and Transgender Children/Youth: Family, Community, and Implications for Practice”, Journal of the American Association of Nurse Practitioners, 28 (10): 521-527.
Belous, C. K., Timm, T. M., Chee, G., Whitehead, M. R. (2012), “Revisiting the sexual genogram”, The American Journal of Family Therapy, 40(4): 281-296.
Boszormenyi-Nagy, I. (2014), Invisible Loyalties, Routledge, London.
Bowen, M., (1980) Key to the use of genogram, in Carter E., McGoldrick M. The family life cicle, Gardner Press, New York.
Budge, S. L., Katz-Wise, S. L., Tebbe, E. N., Howard, K. A., Schneider, C. L., Rodriguez, A. (2013), “Transgender Emotional and Coping Processes Facilitative and Avoidant Coping Throughout Gender Transitioning”, The Counseling Psychologist, 41(4): 601-647.
Butler, J. (2005), La vita psichica del potere, Meltemi Editore, Milano.
Carofiglio G. (2016), Passeggeri notturni, Stile Libero Big Einaudi, Torino.
Cecchin, G., Lane, G., Ray, W. A. (1997), Verità e pregiudizi, Raffaello Cortina, Milano.
Cirillo, S., Selvini, M., & Sorrentino, A. M. (2011), “Il genogramma. Percorso di autoconoscenza, integrato nella formazione di base dello psicoterapeuta”, Terapia Familiare, 95:5-28.
Dallos, R. (1997), Interacting Stories: Narratives, Family Beliefs, and Therapy, Karnac Books, London.
Di Salvo, D (2011), What Makes your Brain Happy and why you Should do the Opposiste, Prometheus Books, New York.
Di Ceglie, D. et al. (2014), “Empathising and Systemising in Adolescents with Gender Dysphoria”, Opticon, 1826 (16): 6 pp. 1-8.
Durkheim, É. (1999), Per una sociologia della famiglia, Armando Editore, Roma.
Green, A. (1983), “La mère morte. Narcissisme de vie, narcissisme de mort”, Critique, Les Éditions de Minuit, Paris, pp. 222-253.
Factor, R. J., Rothblum, E. D. (2008), “A Study of Transgender Adults and their Non-Transgender Siblings on Demographic Characteristics, Social Support, and Experiences of Violence”, Journal of LGBT health research, 3(3): 11-30.
Ferrari, F. (2007), Adolescenza transgender e immagine corporea, in S. Ferrari (a cura di) Il corpo adolescente. Percorsi interdisciplinari fra arte e psicologia, CLUEB, Bologna.
Ferrari, F. (2015), La famiglia inattesa: I genitori omosessuali e i loro figli, Mimesis Edizioni, Milano.
Fruggeri, L. (2001), “I concetti di mononuclearità e plirinuclearità nella definizione di famiglia”, Connessioni, 8:11-22.
Fruggeri, L., (2015), “Sei parole chiave per ricordare Luigi Boscolo”, Connessioni 35: 21-27.
Graglia, M. (2012), Omofobia: strumenti di analisi e di intervento, Carocci Faber, Roma.
Hammond, C., (2013), Il mistero della percezione del tempo, Einaudi, Torino.
Hardy, K. V., Laszloffy, T. A. (1995), “The Cultural Genogram: Key to Training Culturally Competent Family Therapists”, Journal of Marital and Family Therapy, 21.3: 227-237.
Hof, L., Berman, E. (1986), “The Sexual Genogram”, Journal of Marital and Family Therapy, 12(1): 39-47.
Jackson, D. (1967), “The Fear of Change”, Medical Opinion & Review, 3(3): 34-41.
Jolly, W., Froom, J., Rosen, M. G. (1980), “The Genogram”, The Journal of family practice, 10(2): 251-255.
Leone, G., Mazzara, B. M., Sarrica, M. (2013), La psicologia sociale: processi mentali, comunicazione e cultura, GLF editori Laterza, Bari.
Lev, A. I. (2013), Transgender Emergence: Therapeutic Guidelines for Working with Gender-Variant People and their Families, Routledge, London.
Lingiardi, V., Giovanardi, G. (2017), “Di che genere credi di essere?”, in Il Sole 24 ore del 19 Febbraio.
Lupoi, S., Mazzaglia, R., Grasso, C., Breci, E., Cavallaro, L., Gisabella, A., Gnoffo, F. (2002), “Il genogramma evolutivo: dal genogramma alla formazione, dalla formazione al genogramma”, Rivista di psicoterapia relazionale.
Mahler, M. S., Pine, F., Bergman, A. (1975), La nascita psicologica del bambino, Bollati Boringhieri, Torino.
Malpas, J. (2011), “Between Pink and Blue: A Multi‐Dimensional Family Approach to Gender Nonconforming Children and their Families”, Family Process, 50(4): 453-470.
Marchiori, R. (2014), Il genogramma con la doppia linea: premesse, utilizzo e riflessioni in divenire, in Mosconi, A., Pezzolo, M., Racerro, G. (a cura di), Identità Sistemiche, UltimaBooks. http://www.ultimabooks.it/identità-sistemiche.
Marchiori, R. (2013), Dalla doppia linea al genogramma tridimensionale. Creatività e coraggio con le organizzazioni familiari complesse, intervento al Congresso Internazionale S.I.P.P.R. Le risorse della psicoterapia relazionale: teorie, tecniche, condivisione, responsabilità, coraggio, Prato, 7-9 Marzo.
Marchiori, R., Viaro, M. (2015), “Genogramma, cronologia degli eventi, mappa delle relazioni nella formazione e nella clinica: una rivisitazione”, Terapia familiare, 107: 40-58.
Mariotti, G. (2002), “Empatia e comprensione del dolore”, in Fomenti, L., Giusti, M., Mapelli, B., Narrazioni, Quaderno, (3), pp.103-115.
Massara, D., Manzon, M., Cavarretta, M. R., Einaudi, S. (2012), “Crisalide e farfalla. Quale identità?”, Terapia familiare, 98: 21-33.
McCubbin, H. I., Patterson, J. M. (1983), “The Family stress process. The double ABCX model of family adjustment and adaptation”, Marriage and Family Review, 6:7-37.
McGoldrick, M. (2016), The Genogram Casebook. A Clinical Companion to Genogram: Assessment and Intervention, W.W. Norton, New York.
McGoldrick, M., Gerson, R., Shellenberger, S. (1985), Genograms: Assessment and Intervention, Norton & Company, New York.
Menvielle, E. (2012), “A comprehensive program for children with gender variant behaviors and gender identity disorders”, Journal of Homosexuality, 59(3): 357-368.
Monceri, F. (2010), Oltre l’identità. Teorie queer e corpi transgender, Edizioni ETS, Pisa.
Nestle, J., Howell, C., Wilchins, R. A. (eds.) (2002), Genderqueer: Voices from Beyond the Sexual Binary, Alyson Publications, New York.
Olson, D.H., Stewart K. (1990), Multisystem Assessment of Stress and Healh, Model and Stress Profile (HSP), University of Minnesota Press, Minneapolis.
Petiva, P., Spirito, M. (2015), “Generi di prima necessità: terapia familiar di adolescent con disforia di genere”, Terapia familiare, 109: 5-20.
Poggio, B., & Jedlowski, P. (2004), Mi racconti una storia? Il metodo narrativo nelle scienze sociali, Carocci, Roma.
Rigobello, L., Gamba, F. (eds.) (2016), Disforia di genere in età evolutiva. Sostenere la ricerca dell’identità di genere nell’infanzia e nell’adolescenza: Sostenere la ricerca dell’identità di genere nell’infanzia e nell’adolescenza, Franco Angeli, Milano.
Sandri, F., Fiorindo, F., Pascolo-Fabrici, E., Nastasich, S., Trombetta, C. (2013), “Personality profile assesment in patients with gender identity disorder”, Psychology, Community & Health, Vol. 2(2), 259–303.
Sandri, F., et al. (2015), “Gender Disphorya and Personality disorder: an investigation on comorbidity”, Journal of Sexual Medicine, Vol. 12, Wiley-BlackWell, Hoboken NJ.
Sandri, F. (2015), “Saggio sul transessualismo”, Rivista di Sessuologia, Vol. 39, N. 2-3 Maggio-Dicembre, Scione Editore, Roma.
Sandri, F., Bonavigo, T., Marchiori, R., Mosconi, A., Pascolo-Fabrici, E. (2016), “A client-oriented approach to genogram in patients with Gender Disphorya”, Research and Advances in Psychiatry; supp. 1:1-42.
Sandri, F., (2016), La Disforia di Genere, in AA.VV. Oltre la psichiatria. Teorie e pratiche in salute mentale territoriale, EUT, Trieste, pp. 311-316.
Sandri, F., Bonavigo, T., Marchiori, R. (2016), “L’uso del genogramma nella pratica clinica con la persona transessuale: alcune proposte di riflessione”, Rivista di Sessuologia: Disforie di Genere Attualità e prospettive, Vol 40, n 2. pp. 139-155, Scione Editore, Roma.
Sandri, F., Nadalin, D. (2016), “Glossario”, Rivista di Sessuologia: Disforie di Genere Attualità e prospettive, Vol. 40, n 2. pp. 183-189, Scione Editore, Roma.
Saraceno C. (2012), Coppie e famiglie. Non è questione di natura, Feltrinelli Editore, Milano.
Sorrentino, A. M. (2008), “Il genogramma come strumento grafico per ipotizzare il funzionamento mentale del paziente”, Terapia familiare, 88: 59-92.
Turnaturi, G. (2003), Tradimenti. L’imprevedibilità nelle relazioni umane, Feltrinelli Editore, Milano.
Watzlawick, P., Beavin, J. H., Jackson, D. D. (1967), Pragmatics of Human Communication, Norton, New York. Trad. it. Pragmatica della comunicazione umana, Astrolabio, Roma, 1971.
Unofficial English translation of Rappresentazioni di genere, by Federico Sandri, Roberta Marchiori and Tommaso Bonavigo, Connessioni, new series, no. 1 (2017), under a CC BY 4.0 licence. Translation (with the help of artificial intelligence) and layout: Complexe Systémique, November 2026 — the work has been modified under the terms of the licence (biographical notes moved to the header, epigraph in indirect speech). Neither the authors nor the journal are responsible for this translation; the original version prevails.
Unofficial English translation of “Rappresentazioni di genere”, published in Connessioni (2017) under a CC BY 4.0 licence. Made by Complexe Systémique with the help of artificial intelligence, it does not come from the authors or the journal, who are not responsible for its content; the original version prevails.
Read the original articleHow to cite this article
Sandri, F., Marchiori, R., et Bonavigo, T. (2017). Gender representations (Complexe Systémique, Trans.). Complexe Systémique. https://app.complexe-systemique.com/en_GB/articles/gender-representations (Original work published in 2017 in Connessioni, nuova serie, n. 1 (2017); republished in 2017 by Connessioni, https://connessioni.cmtf.it/rappresentazioni-di-genere/)
To go further
- What you need to know about the genogram, a systemic toolThe genogram, a basic tool.
- “How in God’s Name Are We Going to Navigate This?”: Parent Support for Transgender AdolescentsParents facing transition.
- Blossoming Child, Mourning Parent: A Qualitative Study of Trans Children and Their Parents Navigating TransitionTrans children and grieving parents.
Related training courses
 Symposium
État des Lieux: a psychological approach to spaces
Replay of the “État des Lieux” conference (Paris, 16 October 2026): Ivy Daure, Maurizio Frisina, Viola Sallay and Gilbert Pregno on places as a clinical resource. In French.
 Certifying course
Training in Systemic Therapy and Interventions – Cycle 1
Certifying training cycle in systemic therapy and interventions – year 1. Courses, supervision and practice, aligned with EFTA/SFTF. In French.
 Certifying course
Training in Systemic Therapy and Interventions – Cycle 2
Certifying training cycle in systemic therapy and interventions – year 2. Clinical complexity, supervision and practice. EFTA/SFTF aligned. In French.
 Certifying course
Training in Systemic Therapy and Interventions – Cycle 3
Certifying training cycle in systemic therapy and interventions – year 3. In-depth intervention, supervision and practice. EFTA/SFTF aligned. In French.
Related articles
 Blog
Why do we feel we are behind in our lives?
Checking how old Yalom was when he published his first book reassured me. But in which race? A systemic look at the feeling of being behind, and at what we can change together.
 Scientific
The Duogramma®: An innovative methodology for psychotherapy
A map of the couple relationships lived, desired or rejected since childhood: the Duogramma®, its graphic rules and its use in individual therapy.
 Blog
Adult parentification: when being useful becomes a condition for being loved
Why is it sometimes so hard to hand over? Julien Besse explores parentification and parentalisation, acknowledgement and the place we take in our adult relationships.
 Scientific
Decolonizing Supervision: A Critical Race and Queer Theory Framework for Marriage and Family Therapy
Supervision is not neutral: a framework drawing on Critical Race Theory and Queer Theory to name and share power in supervision, with a vignette.
Comments 0
Log in to join the discussion. Log in