Rehabilitation Counseling Bulletin · Family therapy
Family Therapy as an Intervention for Adults With Aphasia and Other Communication Disabilities After Acquired Brain Injury: A Scoping Review
A brain injury upends the whole family, all the more when it deprives one member of part of their speech. Jessica Henihan, Rebecca Henihan and Caroline Jagoe mapped 24 studies of family therapy after acquired brain injury, with input from a psychologist with aphasia. Finding: half the studies exclude people with communication disabilities, often without saying so, and speech and language therapists are almost never involved.
This is a reformatted republication of Family Therapy as an Intervention for Adults With Aphasia and Other Communication Disabilities After Acquired Brain Injury: A Scoping Review, by Jessica Henihan, Rebecca Henihan and Caroline Jagoe, published in Rehabilitation Counseling Bulletin (SAGE) (2025), doi: 10.1177/00343552241236859, under a CC BY 4.0 licence. Prepared by Complexe Systémique in September 2026: the authors’ text is unchanged; the layout has been adapted for reading online, which constitutes a modification of the work under the terms of the licence. The end-of-article declarations are grouped in the notes. This edition was made neither by the authors nor by the publisher, who are not responsible for its content or for any errors. The original version prevails.
Families of PWCD are entitled to the same high-quality therapy as any other family.
Jessica Henihan, Rebecca Henihan and Caroline Jagoe
Abstract
Acquired brain injury (ABI) affects the whole family unit, significantly shifting family roles and relationships, with communication disabilities associated with ABI further compounding these difficulties. Family therapy is offered in situations where family roles have been disrupted, but research on the application of family therapy to families affected by ABI has not been synthesized. This study systematically maps the research on the use of family therapy for people with ABI, identifying to what extent people with communication disabilities (PWCD) are included in the evidence base. A scoping review of primary research was conducted through a systematic search of five multidisciplinary academic databases. A consultation process, involving a person with aphasia, ran alongside the entire research process. Twenty-four studies were included in the final review with four categories of interventions identified. Twelve studies excluded PWCD, 10 potentially doing so due to the communication demands of the study. Twelve studies included PWCD, five of which included speech and language therapists to support the delivery of family therapy. A small evidence base exists for the use of family therapy within an ABI population. However, PWCD are frequently excluded from this research due to the communication demands of the study designs. More research is needed to guide appropriate intervention for PWCD.
Keywords: acquired brain injury, family therapy, aphasia, family interventions, communication disabilities
Acquired brain injury (ABI) affects the whole family unit, not just the individual (Dawes et al., 2022). ABI can significantly shift family roles and relationships causing an intense effect on emotional, mental, and social well-being within the family system (McDermott & McDonnell, 2013). These difficulties are likely to be compounded where the ABI is associated with a communication disability. Communication disability is defined as an impairment in the functions of speech, language, or cognition, which affects a person’s ability to understand others or to be understood by others (adapted from Washington Group on Disability Statistics, 2016). Communication is one of the core components of family life, with family functioning being reliant on the successful communication of emotions and information. Therefore, disruptions to this communicative process affect how relatives interact with one another (Olson & Gorall, 2003).
Impact of ABI on Family Life
Family members play a crucial role in assisting and aiding their loved ones after an ABI. They often provide emotional care and support for the psychosocial aspects of ABI (Klonoff, 2014). When a person sustains an ABI, families encounter a multitude of difficulties throughout each stage of recovery. It can have an intense effect on the immediate and extended family unit and has substantial consequences on emotional, mental, and social well-being within the family system (McDermott & McDonnell, 2013). Family members may be required to take on new roles such as assisting the person with ABI to complete daily activities and providing financial support (Larøi, 2003). These changes are an important consideration as family is structured around the assistance, management, care, and socialization of each individual in the unit (Galvin et al., 2016). Unfortunately, emotional support is often not available for people with ABI or their family (Larøi, 2003).
Research on the impact of ABI on families has primarily concentrated on primary caregivers. The limited research which has been conducted on children of parents with ABI has shown that children have increased emotional and behavioral difficulties. Children have identified feelings of grief, loss, and worries surrounding familial breakdown, while also having additional responsibilities and independence. They often find it difficult to process and manage these emotions (Charles et al., 2007). Families have identified disparities in supports offered after ABI (Dawes et al., 2022), and affected families have emphasized the necessity of emotional support such as family support groups or family therapy (Bellon et al., 2015).
As family life is based on communication, roles are discussed and negotiated between family members. Disruptions to this communicative process affect how relatives interact with one another (Olson & Gorall, 2003). The limited literature exploring acquired communication disabilities and family relationships focuses on aphasia. Aphasia is a communication disability, primarily caused by stroke, that affects language comprehension and expression, which may impact a person’s interactions, relationships, and quality of life (Berg et al., 2022). For example, people with aphasia often experience adjustments to their role as a parent. The role of parenting is reliant on parent–child communication (Cava et al., 2014; Levin et al., 2012; Romero-Abrio et al., 2019) and effective parent–child communication is associated with increased life satisfaction and emotional well-being for the entire family (Levin et al., 2012). The nature of communication disability means that parents with aphasia may have difficulty reasserting their role as a parent to support their children and alters the allocation of parenting responsibilities between the people with the communication disability (PWCD) and their partners (Manning et al., 2021). Similar difficulties in navigating other family roles may also be experienced, including the relationship between spouses (Stead & White, 2019) and adult siblings (Barrow, 2008).
Limited research in the area of family roles and communication disability has highlighted the disruption of roles within families. Family therapy has the potential to address these adjustments in roles. However, a synthesis of existing evidence is overdue.
Family Therapy
Family therapies are grounded in systems theory. A system, in the context of family, is a collection of people who each have a unique role which is sustained by their interaction with one another (Smith-Acuña, 2010). If there is a change to the structure or roles within the family, such as the impact of a traumatic event (in this case ABI), it can impact significantly on each member. In response, each person’s behavior and role may be altered, shifting the family dynamic. Consequently, intervention is required when one or more roles in the family have changed and disrupted the family dynamic (Walker & Akister, 2004).
Family therapy can occur in different formats, including therapy for the main caregiver, marriage counseling, individual family therapy (for all members), and group therapy where several families are present (Florian & Katz, 1991; Klonoff & Koberstein, 2010; Kreutzer et al., 2002; Rosenthal & Young, 1988). Family therapy is most traditionally provided by family therapists (Klonoff & Koberstein, 2010). However, in some contexts, it may be within the scope of practice for other healthcare providers to support the readjustment of roles (Hodgson et al., 2014; Marlowe, 2011; Rolland & Walsh, 2005; Tyndall et al., 2012). The involvement of speech and language therapists (SLTs) in the delivery of family therapy may be particularly relevant in the context where a family member has a significant communication disability.
To date, there has been no systematic synthesis of how family therapy interventions have been applied to an ABI population. Furthermore, it is unknown to what extent PWCD, associated with ABI, have been included in family therapy interventions. This study systematically maps the research on family therapy for people with ABI, identifying to what extent PWCD are included in the evidence base. The review was guided by the following research questions: (a) What evidence exists for the use of family therapy in an adult ABI population? and (b) are PWCD included in the evidence base?
Method
The research questions were addressed through a scoping review using the six-step framework developed by Arksey and O’Malley (2005). The broad research questions and the large amount of evidence in this area, in addition to the wide variety of variables, suggested the use of a scoping review. This methodology allowed the researchers to scope the breadth of the literature, allowing for an overview of the prominent concepts and theories that act as the foundation to a research area (Mays et al., 2001). Additionally, the evidence synthesis that is the result of a scoping review can inform both evidence-based practice and clinical practice (Gough et al., 2020).
First, the six-step framework began with “identifying the research question,” as the research questions directed the manner in which search strategies were created. Second, “identifying relevant studies” involved finding research which appropriately addressed the research questions. This step required the identification of key databases and the generation of search strategies to find relevant studies. Third, “study selection” comprised identifying inclusion and exclusion criteria which enabled the exclusion of research which did not answer the research questions. The fourth step involved “charting the data” by synthesizing the results according to key information presented in each study. The fifth step, “collating, summarizing, and reporting the results,” provided readers with a narrative overview of the results. Finally, an optional sixth step of a “consultation process” utilizing stakeholder groups to provide professional experience was adapted and used (Arksey & O’Malley, 2005). Further details on how these steps were carried out are described in each section below.
Additionally, the PRISMA-ScR guidelines (a 20-step checklist detailing reporting steps for scoping reviews) were consulted and reported against in this research. These guidelines aim to provide methodological transparency and replicability (Tricco et al., 2018).
Consultation Process
The optional consultation process used in this research was not the traditional broad stakeholder group as described by Arksey and O’Malley (2005). Instead, consultation was sought and received from a co-researcher who is a psychologist and has aphasia post-ABI. The inclusion of a researcher with professional and living experience in this research area affords an opportunity for a unique perspective to be included. Consequently, this method ensures that research is both relevant and meaningful to those whom it is centered on (Hersh et al., 2021). The co-researcher was involved throughout the entire scoping review process. Starting with the question formulation, the co-researcher provided a degree of initial consultation, acting as a sounding board and describing their own experience of a communication disability and role changes within their family system. Once the research questions had been formulated, the co-researcher completed title/abstract screening and piloting data extraction forms with the primary researcher. As the co-researcher is an expert in their own right in this area, they were consulted during the results and discussion sections to provide a unique and personal insight. Finally, the co-researcher was consulted about directions for future research to highlight the issues that PWCD may face when accessing these interventions.
Identifying Relevant Studies
In accordance with the PRISMA-ScR guidelines, search strings were developed to identify significant evidence and articles related to the research questions (Tricco et al., 2018). The initial search string was devised with the assistance of a subject librarian and was comprised of title/abstract keywords and controlled vocabulary. The search strings were piloted and modified using key concepts from the research questions (e.g., family therapy, brain injury, etc.). To ensure that any papers focusing on communication diagnoses associated with ABI were not missed, the three most common diagnoses were included in the search strings, namely: aphasia, dysarthria, and cognitive communication disorders.
Searches were completed across five databases (PubMed, Embase, CINAHL Complete, Web of Science, and PsycINFO), reflecting the multidisciplinary nature of the research questions. All published articles were included with no restrictions on publication date. The final search strings for each database are shown in Table 1.
Table 1 — Search Strings.
- Databases: PubMed; Search strings: ((“Family Therapy”[Mesh]) OR (family therap*[Title/Abstract])) AND ((“Brain Injuries” [Mesh]) OR “Aphasia” [Mesh] OR “Dysarthria” [Mesh] OR (brain injur*[Title/Abstract] OR stroke*[Title/Abstract] OR cerebrovascular accident*[Title/Abstract] OR head injur*[Title/Abstract] OR intracranial injur*[Title/Abstract] OR brain trauma*[Title/Abstract] OR brain damage*[Title/Abstract] OR concussion*[Title/Abstract] OR penetrating skull fracture*[Title/Abstract] OR aphasia*[Title/Abstract] OR dysarthria*[Title/Abstract] OR cognitive-communicat*[Title/Abstract]))
- Databases: Embase; Search strings: (“family therapy”/exp OR “family therap*”: ab, ti) AND (“brain injury”/exp OR “aphasia”/exp OR “dysarthria”/exp OR “brain injur*”: ab, ti OR stroke*:ab,ti OR “cerebrovascular accident*”: ab, ti OR “head injur*”: ab, ti OR “intracranial injur*”: ab, ti OR “brain trauma*”: ab, ti OR “brain damage*”: ab, ti OR concussion*:ab,ti OR “penetrating skull fracture*”: ab, ti OR aphasia*:ab,ti OR dysarthria*: ab, ti OR “cognitive-communicat*”: ab, ti) AND ([embase]/lim NOT [medline]/lim)
- Databases: CINAHL Complete; Search strings: ((MH “Family Therapy” OR (TI Family therap*) OR AB (Family therap*)) AND ((MH “Brain Injuries+” OR (MH “Aphasia+”) OR (MH “Dysarthria+”) OR TI (brain injur* OR stroke* OR cerebrovascular accident* OR head injur* OR intracranial injur* OR brain trauma* OR brain damage* OR concussion* OR penetrating skull fracture* OR aphasia* OR dysarthria* OR cognitive-communicat*) OR AB (brain injur* OR stroke* OR cerebrovascular accident* OR head injur* OR intracranial injur* OR brain trauma* OR brain damage* OR concussion* OR penetrating skull fracture* OR aphasia* OR dysarthria* OR cognitive-communicat*))
- Databases: Web of Science; Search strings: (TS=(“family therap*”)) AND TS=(“brain injur*” OR stroke* OR “cerebrovascular accident*” OR “head injur*” OR “intracranial injur*” OR “brain trauma*” OR “brain damage*” OR concussion* OR “penetrating skull fracture*” OR “aphasia*” OR “dysarthria*” OR “cognitive-communicat*”)
- Databases: PsycINFO; Search strings: ((DE “Family Therapy” OR DE “Conjoint Therapy” OR DE “Strategic Family Therapy” OR DE “Structural Family Therapy”) OR TI (family therap*) OR AB (family therap*)) AND ((DE “Brain Injuries” OR DE “Traumatic Brain Injury” OR DE “Brain Concussion” OR DE “Aphasia” OR DE “Dysphasia” OR DE “Dysarthria”) OR TI (brain injur* OR stroke* OR cerebrovascular accident* OR head injur* OR intracranial injur* OR brain trauma* OR brain damage* OR concussion* OR penetrating skull fracture* OR aphasia* OR dysarthria* OR cognitive-communicat*) OR AB (brain injur* OR stroke* OR cerebrovascular accident* OR head injur* OR intracranial injur* OR brain trauma* OR brain damage* OR concussion* OR penetrating skull fracture* OR aphasia* OR dysarthria* OR cognitive-communicat*))
Note: ABI = acquired brain injury; HSCP = health and social care professional.
Study Selection
The final search was completed on October 5, 2021. The search results were imported to the systematic review manager Covidence (2021), and duplicates were removed. Title and abstract screening was conducted by reading through all abstracts and assessing their relevance in relation to the inclusion and exclusion criteria (see Table 2). To ensure replicability, 10% (n = 52) of the articles were also screened by a co-researcher. No disagreements occurred.
Table 2 — Inclusion and Exclusion Criteria for Scoping Review.
- Inclusion criteria: Family-oriented therapy to promote adjustment within the family or have well-being as an outcome; Exclusion criteria: Family-oriented therapy which does not address areas of adjustment within the family or have well-being as an outcome
- Inclusion criteria: Family therapy given by a trained professional (e.g., psychotherapist or HSCP)
- Inclusion criteria: People diagnosed with ABI who are over the age of 18 years; Exclusion criteria: People diagnosed with ABI who are under the age of 18 years
- Inclusion criteria: People with or without a communication disability who have ABI; Exclusion criteria: Any person diagnosed with a progressive neurological condition
- Inclusion criteria: People identified as family of people with ABI; Exclusion criteria: People not identified as family of people with ABI (colleagues, friends, etc.)
- Inclusion criteria: Studies from any country, written in English
- Inclusion criteria: Studies conducted within any time period
- Inclusion criteria: Published journal articles; Exclusion criteria: Gray literature (reports, theses, etc.)
- Inclusion criteria: Primary research; Exclusion criteria: Secondary research
Note. ABI = acquired brain injury; SLT = speech and language therapist.
Study participants had to meet the criteria of (a) an adult with a diagnosis of ABI or (b) people identified as family of people with an ABI. Studies that included people with a progressive neurological condition were excluded. For the purposes of this study, an adult with ABI was defined as above the age of 18, but family members could be of any age (see Table 2). Interventions within the area of family-oriented therapy, whether given by a trained family therapist or given by another healthcare professional, were included in the review (see Table 2). Articles that reported on outcome data, such as well-being or adjustment within the family as a result of family therapy, were included (see Table 2).
The screened articles were subjected to full-text screening to decide whether they met the inclusion criteria for the review. Full-text articles that met the eligibility criteria were included in the final review. To locate articles not found in the initial search, all reference lists of articles included in the final review were manually searched. This was completed by reading each article title and using inclusion/exclusion criteria to assess its suitability for inclusion. No additional articles were identified through reference list searching.
Charting the Data
This stage of the scoping process required the extraction and charting of significant areas of data from articles that were included in the final review. The researcher developed a data extraction form a priori. Two members of the research team trialed the data extraction form using 25% (n = 6) of the articles, to assess its suitability to answer the research questions (Daudt et al., 2013; Levac et al., 2010). Each article was picked in random order and the data was extracted according to the sequence outlined on the data extraction form. No adjustments were made following the piloting of the form.
The data extraction form organized the data according to central themes. A narrative review approach was used for synthesis, as it allowed the researcher to note information about the process of an intervention, so context could be provided when describing the outcome (Arksey & O’Malley, 2005). The data extracted from each article included:
- I. Study characteristics (Author(s), year of publication, study location, study design, aims, methodology, language, no. of participants, age, and gender);
- II. Intervention and outcomes (Intervention type, focus of the intervention, frequency of sessions, professions delivering the intervention, study populations, outcome measures, and intervention outcomes);
- III. Presence/absence of PWCD (Nature and severity of communication disability, and rationale for inclusion/exclusion of PWCD).
To ensure that the presence or absence of PWCD was accurately recorded for each study, the use of three labels, similar to the ones used by Jagoe et al. (2021), was considered. The label “included” was used when a study explicitly stated that PWCD were involved. Second, “excluded” was utilized when a study explicitly stated the exclusion of PWCD. For studies that did not explicitly state the exclusion of PWCD, but where a critical review of the communication demands in the study implied that they were likely to be excluded, the label “potentially excluded due to the communication demands of the study” was used.
Collating, Summarizing, and Reporting the Results
This step involved organizing, summarizing, and discussing the results (Arksey & O’Malley, 2005). First, a quantitative analysis of the amount, description, and distribution of the evidence was collated. Second, a synopsis of all the studies reviewed was created. Third, evidence was reported according to the types of therapy intervention, the professionals providing the therapy, and the outcomes of the intervention.
Findings
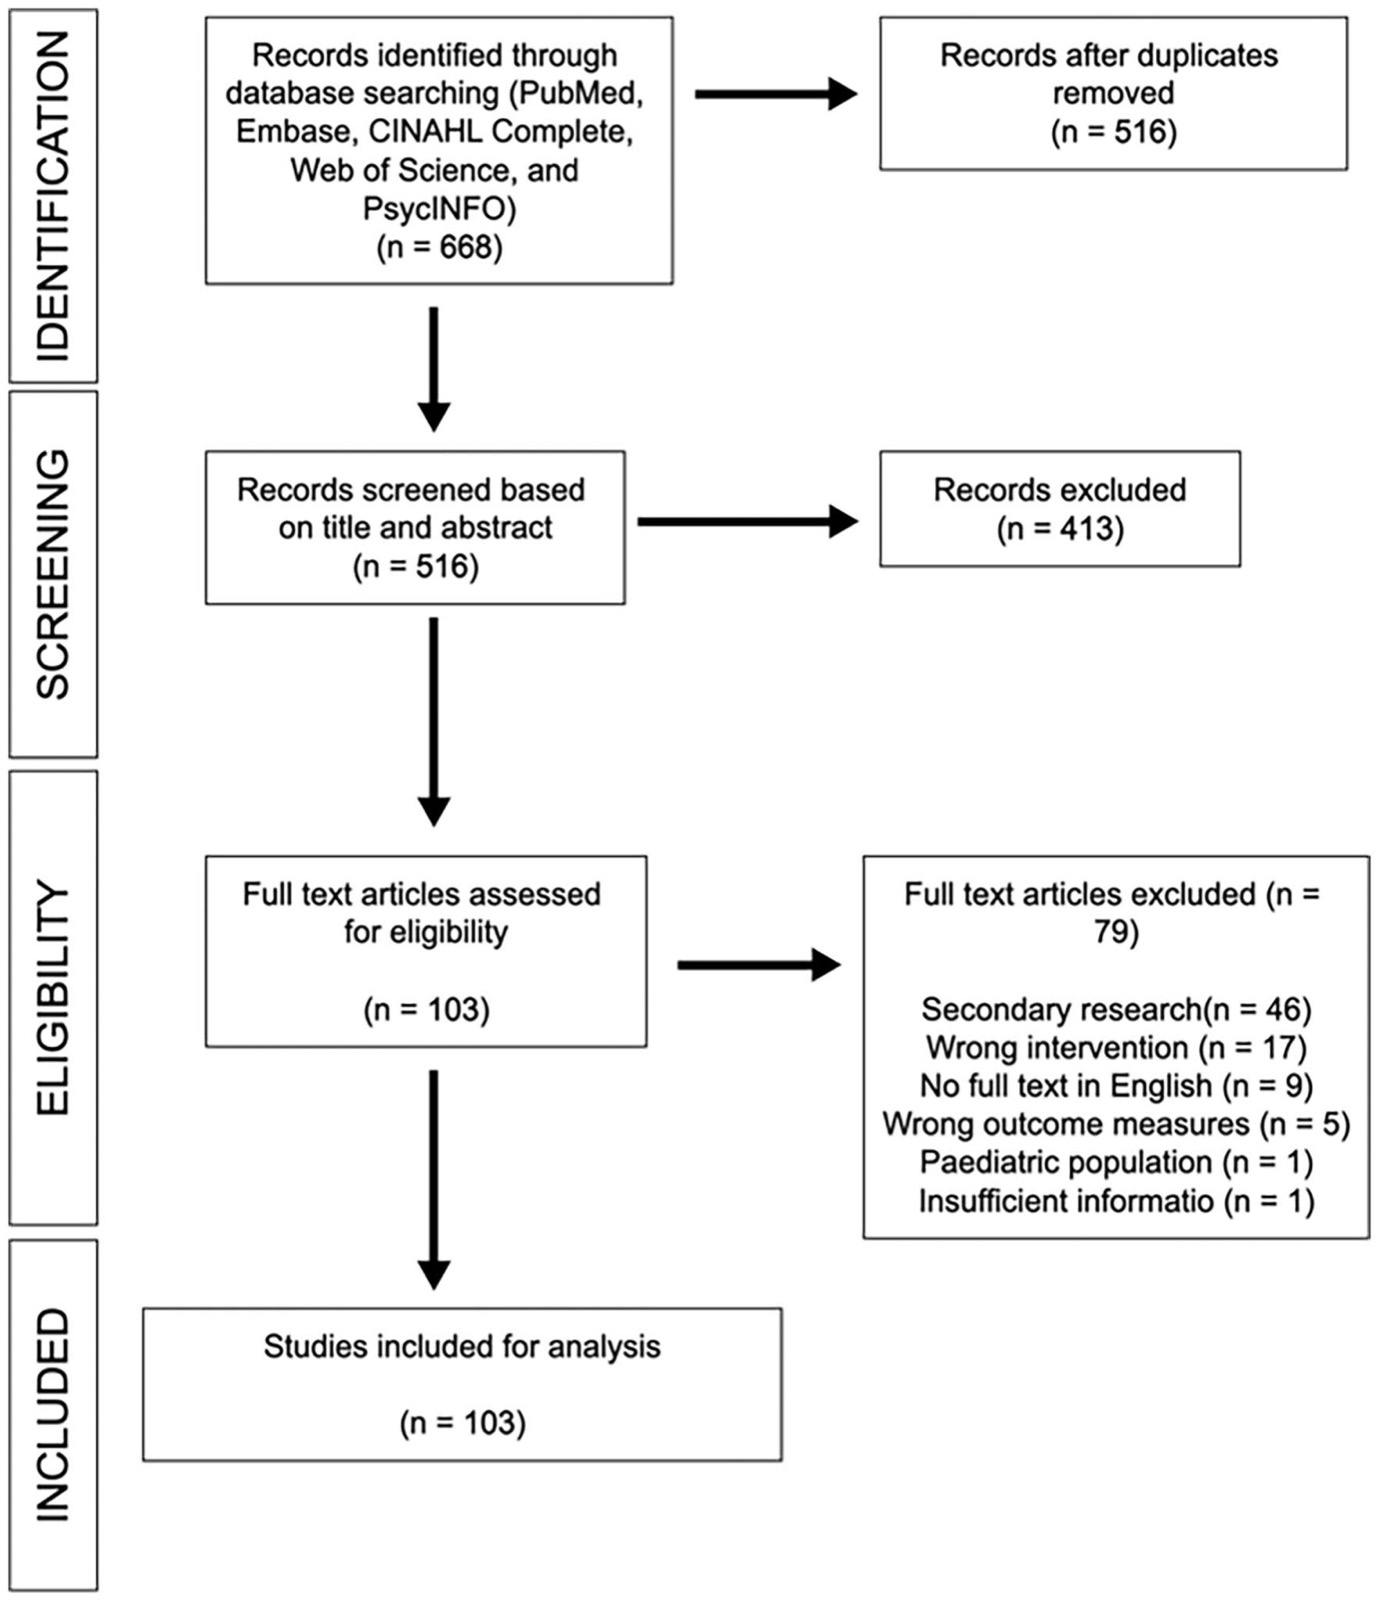
The search process identified 668 articles through electronic database search, with 516 articles remaining after de-duplication. In total, 24 studies met the criteria for inclusion in the scoping review (see Figure 1).
Study Characteristics
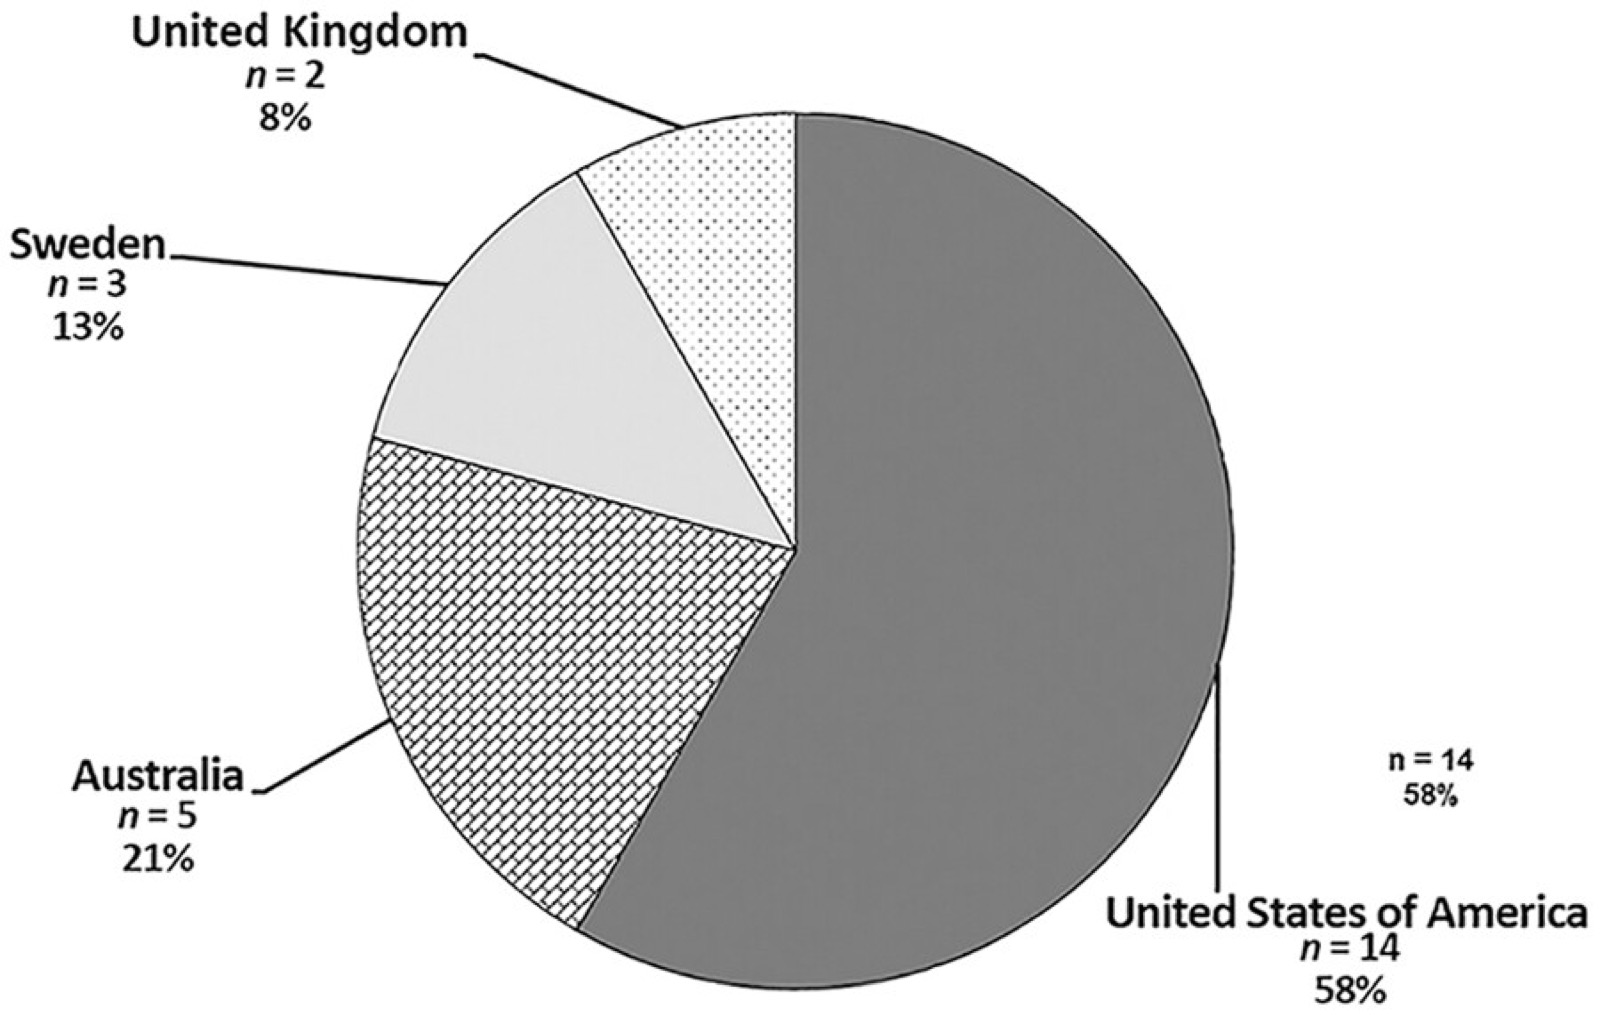
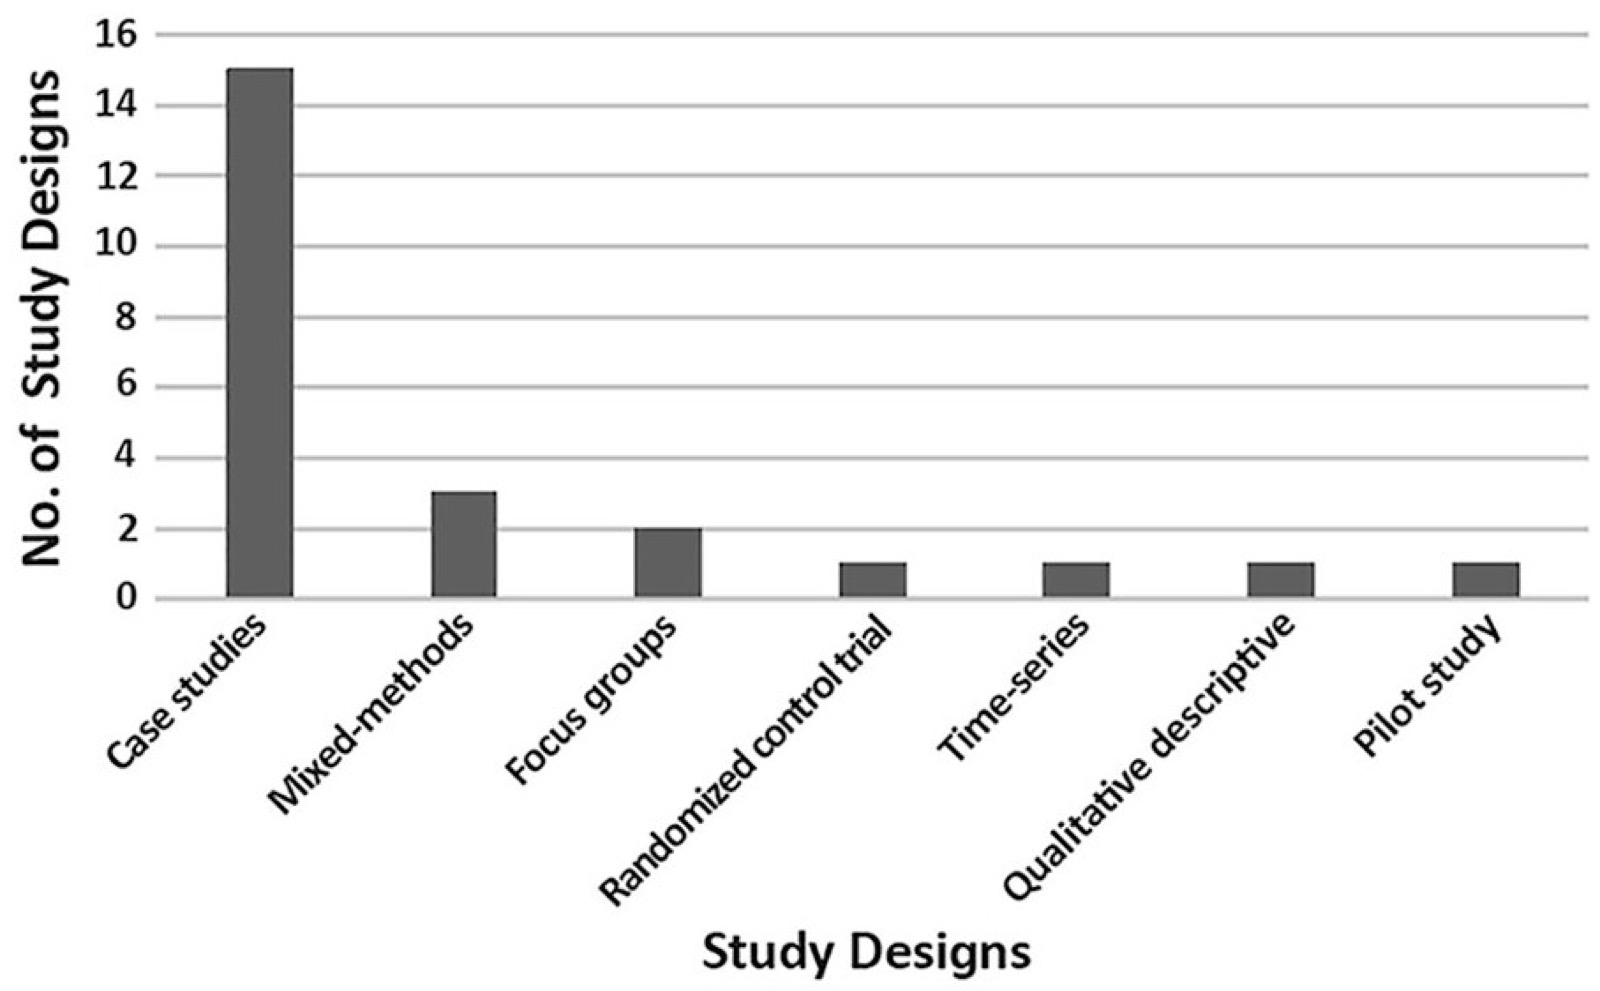
The 24 studies were published between 1952 and 2019. The articles were published across four countries: 58.3% (n = 14) in the United States, 20.8% (n = 5) in Australia, 12.5% (n = 3) in Sweden, and 8.3% (n = 2) in the United Kingdom (see Figure 2). The majority of articles had a case study design (n = 15; 62.5%), followed by mixed methods (n = 3; 12.5%), and then focus groups (n = 2; 8.3%). The remaining four articles had differing study designs (n = 4; 16.7%) which included a randomized control trial, a time series, a qualitative descriptive study, and a pilot study (see Figure 3). All the articles were written in English with the majority of interventions being conducted through English too. Swedish was used as the main language for intervention in three studies (Studies 2, 5, and 21; see Appendix). One study did not report the number of people participating in the intervention with the remaining studies reporting between 2 and 152 participants.
Family Therapy Interventions
The included articles in this review centered on four main types of family therapy interventions for people with ABI and their family, namely: psychoeducation (n = 4; 16.7%), traditional family therapy (n = 8; 33.3%), family therapy adapted for people with ABI (n = 10; 41.7%), and psychosocial interventions (n = 2; 8.3%).
Psychoeducation Interventions (Studies 1–4):
provided information on the nature and rehabilitation process of ABI including acquired communication disorders associated with ABI (see Appendix). These studies provided emotional support to deal with adjustment of roles and responsibilities and to improve family functioning. Professionals who were involved in delivering this style of intervention included: joint working between a psychologist and SLT (Study 1), an SLT working independently (Study 2), a social worker working independently (Study 3), and a multidisciplinary team (Study 4; see Table 3). The frequency of sessions was recorded in three of the studies (Studies 2–4). The frequency ranged from weekly sessions over 6 weeks (Study 2), to 3 sessions over 5 months (Study 3), and bimonthly sessions over 5 months (Study 4). Outcome measures used included: self-reported measures (Study 1), the McMaster Family Assessment Device (Epstein et al., 1983) (Study 3), and questionnaires (Studies 2 and 4). These four studies showed improvements in the participants’: (a) awareness of the impact of ABI and communication disabilities (Studies 2 and 4); (b) understanding of family roles and responsibilities (Studies 1–3); (c) ability to advocate for family members with ABI (Study 4); (d) ability to recognize the importance of emotional support during this time (Studies 2 and 4); and (e) attitudes toward healthcare professionals (Study 4). One of the studies reported a reduction in feelings of anxiety and guilt associated with ABI (Study 1). Another study showed that family therapy had no substantial effects on depression for the person with ABI (Study 3; see Appendix).
Table 3 — Range of Professionals Delivering Family Therapy.
- Professionals giving therapy: Psychologist only; No. of studies: 6; Intervention type: ● Traditional family therapy
● Family therapy adapted for people with ABI; Study identifier: 7, 9, 10, 13, 14, 16 - Professionals giving therapy: Family therapists only; No. of studies: 4; Intervention type: ● Traditional family therapy
● Family therapy adapted for people with ABI; Study identifier: 6, 8, 11, 15 - Professionals giving therapy: Multidisciplinary team; No. of studies: 3; Intervention type: ● Psychoeducation
● Family therapy adapted for people with ABI
● Psychosocial therapy; Study identifier: 4, 20, 24 - Professionals giving therapy: Psychiatrists only; No. of studies: 2; Intervention type: ● Family therapy adapted for people with ABI; Study identifier: 18, 19
- Professionals giving therapy: Psychotherapists only; No. of studies: 2; Intervention type: ● Family therapy adapted for people with ABI; Study identifier: 21, 22
- Professionals giving therapy: SLT and psychologists; No. of studies: 2; Intervention type: ● Psychoeducation
● Traditional family therapy; Study identifier: 1, 5 - Professionals giving therapy: SLT only; No. of studies: 1; Intervention type: ● Psychoeducation; Study identifier: 2
- Professionals giving therapy: SLT and family therapists; No. of studies: 1; Intervention type: ● Traditional family therapy; Study identifier: 12
- Professionals giving therapy: Social Worker; No. of studies: 1; Intervention type: ● Psychoeducation; Study identifier: 3
- Professionals giving therapy: People with ABI and their family members; No. of studies: 1; Intervention type: ● Psychosocial therapy; Study identifier: 23
- Professionals giving therapy: Psychologists and social workers; No. of studies: 1; Intervention type: ● Family therapy adapted for people with ABI; Study identifier: 17
Note. PWCD = people with a communication disability; PWA = people with aphasia; SLT = speech and language therapist; CPT = communication partner training; ABI = acquired brain injury; SLP = speech and language pathologist; HSCP = health and social care professional; TBI = traumatic brain injury.
Traditional family therapy interventions (Studies 5–12):
enabled people with ABI to acknowledge their injury, educated their family on the injury, improved interpersonal relationships within the family, and identified and redefined roles and responsibilities. Additionally, these studies explored the shifts in relationships caused by ABI and aphasia and provided skills to cope with these shifts (see Appendix). Professionals who were involved in delivering traditional family therapy included: joint working between a psychologist and SLT (Study 5), a family therapist working independently (Studies 6, 8, and 11), a psychologist working independently (Studies 7, 9, and 10), and joint working between a family therapist and SLT (Study 12; see Table 3). The frequency of sessions was recorded in six of the studies (Studies 5, 6, 8, 9, 11, and 12). There were a range of frequency of sessions which included: a 5-day course (Study 5), unlimited sessions for the duration of the research (Studies 6 and 8), biweekly sessions over 12 months (Study 9), 21 sessions over 9 months (Study 11), and 5 therapy sessions over the study period (Study 12; see Appendix). Outcome measures used to evaluate intervention efficacy included: self-reported outcomes (Studies 7–11), questionnaires (Studies 5 and 12), and the Family Environment Scale (Moos & Moos, 1981) (Study 6). Traditional family therapy: (a) improved quality of life, family cohesion, negotiation of parental roles/experiences, emotional skills, sense of pride and accomplishment with hope for the future (Studies 5–10) and (b) reduced distress, caregiver burden, and family conflict (Studies 6, 11, and 12; see Appendix).
Family therapy adapted for people with ABI (Studies 13–22):
provided psychological support to manage the effects of ABI, improved communication within families across all levels of interaction, and helped the family to adjust their expectations of roles and responsibilities. Professionals who were involved in delivering family therapy adapted for people with ABI included: a psychologist working independently (Studies 13, 14, and 16), a family therapist working independently (Study 15), joint working between psychologists and social workers (Study 17), a psychiatrist working independently (Studies 18 and 19), a multidisciplinary team (Study 20), and a psychotherapist working independently (Studies 21 and 22; see Table 3). The frequency of sessions was recorded in seven of the studies (Studies 13, 14, and 16–20). There were a range of frequency of sessions which included: biweekly sessions over 10 weeks (Study 13), weekly sessions over 12 weeks (Study 14), 5 sessions over the duration of the study (Study 16), 20 sessions over 2 years (Study 17), bimonthly sessions over 9 months (Study 18), 3 sessions over the duration of the study (Study 19), and unlimited sessions over 7 months (Study 20; see Appendix). Outcome measures utilized involved: self-reported outcomes (Studies 15–17, 20, and 22), focus groups (Studies 14 and 19), the Family Empowerment Scale (Koren et al., 1992) (Study 18), and questionnaires (Studies 13 and 21). These studies showed that: (a) patients and caregivers benefited from these interventions (Studies 13–22); (b) there were improvements in the negotiation and reclamation of familial roles and responsibilities, and improved success, pride, and empowerment (Studies 14–18 and 21); (c) there was increased acceptance of the effects of ABI (Study 20); and (4) there was reduced conflict, caregiver burden, and isolation (Studies 14 and 17–19). Overall, these interventions greatly improved the participant’s quality of life.
Psychosocial therapy interventions (Studies 23 and 24):
focused on community support for people with ABI and their families and strengthening romantic relationships. Professionals involved in delivering psychosocial therapy included: people with ABI and their family members (Study 23), and a multidisciplinary team (Study 24; see Table 3). The frequency of sessions varied from unlimited sessions over 1 year (Study 23), to 15 sessions over 24 weeks (Study 24). Outcome measures addressing these aims included retrospective structured interviews (Study 23) and self-reported outcomes (Study 24). The outcomes of these interventions demonstrated: (a) an increased knowledge of the effects of ABI (Studies 23 and 24); (b) an improved quality of life, family mood, and cohesion (Study 23); (c) increased pride in accomplishments (Study 24); and (d) strengthened bond between couples, increasing their affection and appreciation of one another (Study 23; see Appendix).
Communication Disabilities and Family Therapy
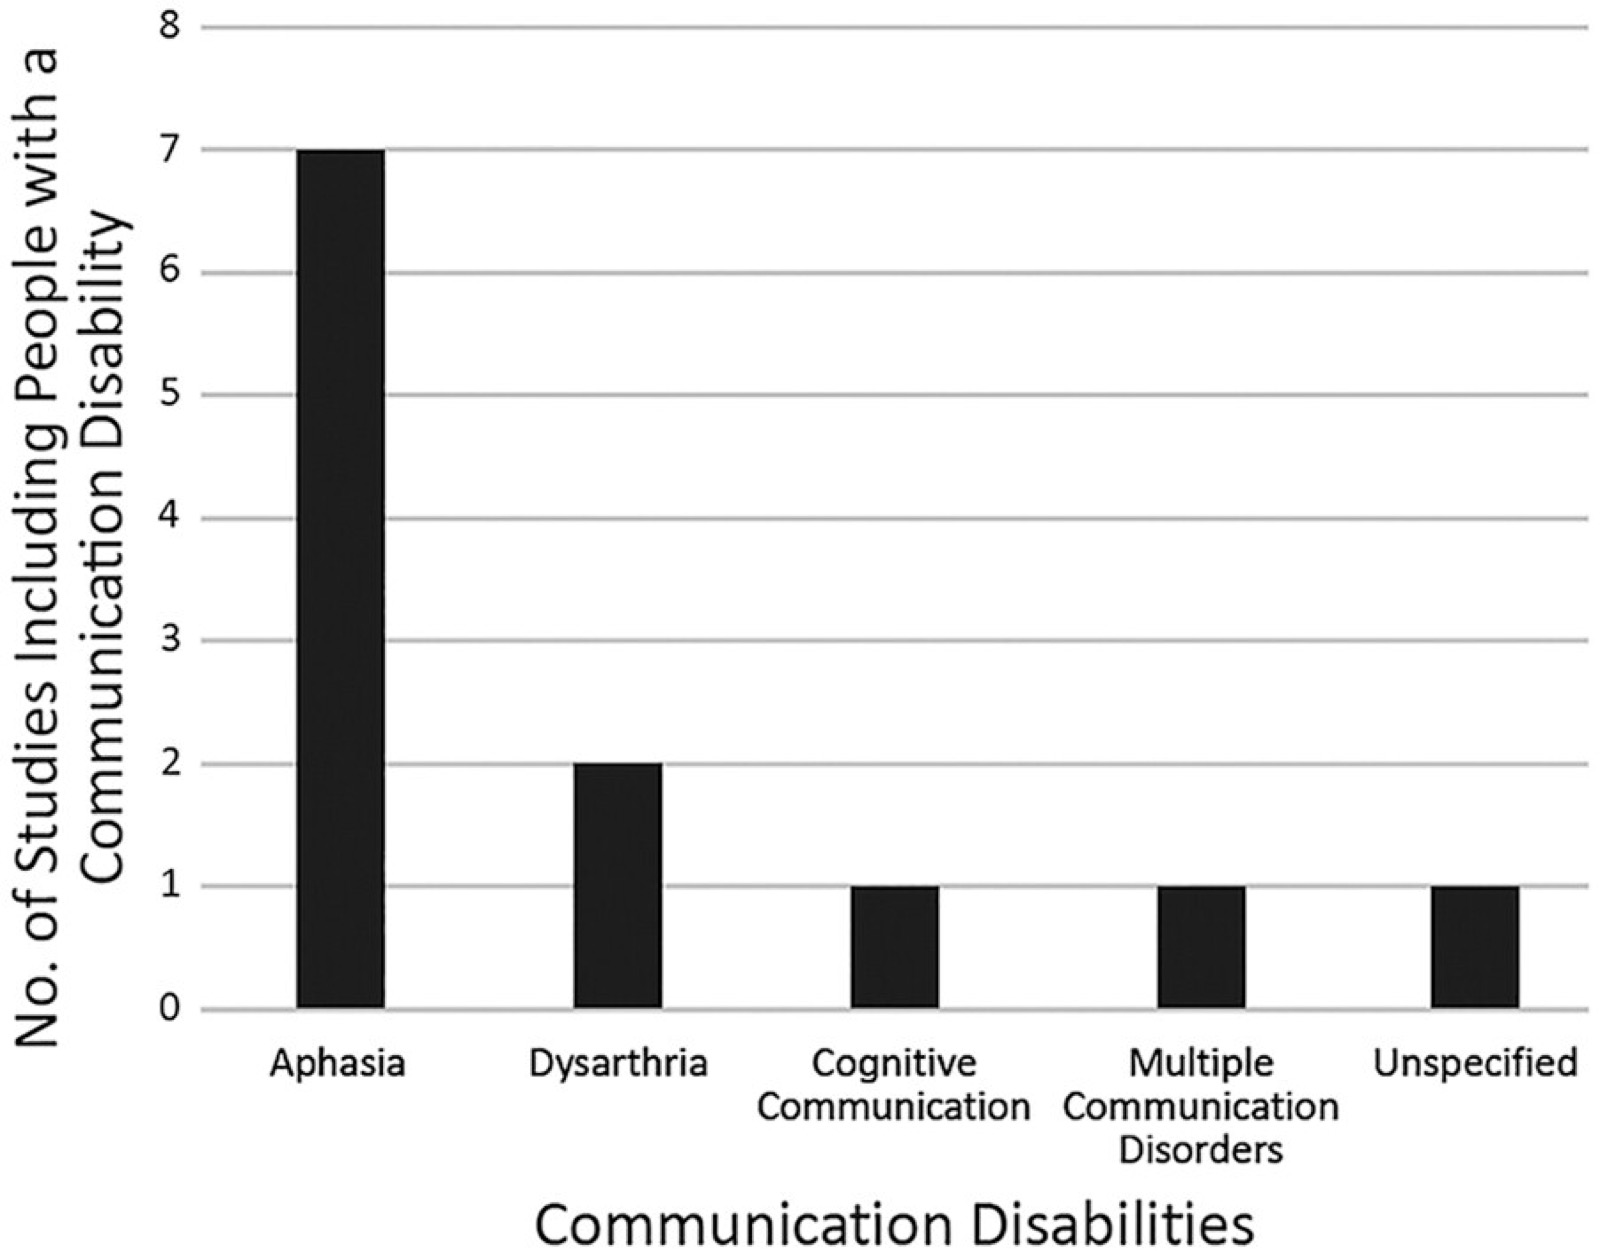
PWCD were included in 50% (n = 12) of the studies (1, 2, 4, 5, 9, 12, 15–17, and 20–22). Aphasia was the most common communication disability present in the studies, with 29.3% (n = 7 of the 24 studies) of all the studies including people with aphasia (Studies 1, 2, 5, 12, 17, 20, and 21). The study designs which included people with aphasia were case studies or time-series designs. These studies delivered psychoeducation (n = 2), traditional family therapy (n = 2), and family therapy adapted for people with ABI (n = 3). People with dysarthria were included in 8.3% (n = 2 of the 24 studies) of the studies (Studies 16 and 22). These studies were case study designs and delivered family therapy adapted for people with ABI. People with cognitive communication disorders were included in one study with a case study design and delivered family therapy adapted for people with ABI (Study 9). One study included people with aphasia, dysarthria, and cognitive communication disorders (Study 15) and utilized a mixed-method study design. This study delivered family therapy adapted for people with ABI. Another study explicitly stated the inclusion of people with any communication disability (Study 4; see Figure 4). Using a case study methodology, this research provided psychoeducation as its intervention to support families post-ABI.
This scoping review identified that half of the total studies (n = 12) did not include PWCD, with 2 studies explicitly excluding these participants (Studies 3 and 24) and 10 studies potentially excluding this cohort due to the communication demands of the study (Studies 6–8, 10, 11, 13, 14, 18, 19, and 23). The study designs employed were case studies (n = 5), mixed-method design (n = 3), focus groups (n = 2), pilot studies (n = 1), and a randomized control trial (n = 1). The majority of these interventions utilized traditional family therapy (n = 5), followed by family therapy adapted for people with ABI (n = 4), psychosocial interventions (n = 2), and psychoeducation (n = 1).
Discussion
The aim of this scoping review was to systematically map the research that has been conducted on family therapy in the context of ABI, identifying the extent to which PWCD are included in the evidence base. This review highlights how the specific needs of those who have communication disabilities are underrepresented in the literature, thereby risking inequality of evidence-based care.
The scoping review process identified 24 studies providing family therapy for families where one person has ABI. Despite the prevalence of communication disability after ABI, half of the studies did not include families where one member had a communication disability. Only two of these studies explicitly reported the exclusion of PWCD (Clark et al., 2003; Glass et al., 2000). The remaining 10 studies were recorded as potentially excluding PWCD due to the communication demands of the study, thereby supporting the assertion that there remains a lack of evidence-based psychological interventions for PWCD (Baker et al., 2019). These findings also resonate with Townend et al.’s (2007) results which found that only 3% of studies using interventions to address stroke and depression explicitly stated the exclusion of people with aphasia.
Overall, the studies reported that participants’ quality of both personal and family life was improved post-intervention. The majority of outcome measures used in the studies were self-reported outcomes from either participants or clinicians. When formal measures were utilized in the studies, there was variability in the type of measures used. Consequently, it was difficult to draw similarities and differences between studies. Reporting of the inclusion or exclusion of PWCD in family therapy research should be clearer, with disaggregated data provided within published articles to increase the generalizability of the results. Providing this type of data will support the application of these results to clinical practice with PWCD.
There were a wide range of professionals who delivered family therapy interventions for people with ABI, with psychologists and family therapists delivering the majority of interventions. While half of the studies included PWCD, only five studies included an SLT (Blom Johansson et al., 2013; Borenstein et al., 1987; Lauer-listhaus, 1991; Nichols et al., 1996; Turnblom & Myers, 1952), with one study involving an SLT delivering the intervention independently (Blom Johansson et al., 2013). Where SLTs were involved in family therapy including PWCD, the studies reported on the use of specific interventions which did not solely rely on verbal communication for participation. The dearth of SLTs included in this research process may be attributed to a lack of understanding of their role by other healthcare professionals. This gap in SLT involvement has been recognized in the literature addressing the role of SLTs in palliative care (Hawksley et al., 2017), dementia care, (Dooley & Walshe, 2020), and the collaboration of educational psychologists and SLTs (Dunsmuir et al., 2006), suggesting that this issue is prevalent across a range of multidisciplinary contexts.
Implications for Practice
Families of PWCD are entitled to the same high-quality therapy as any other family. The communication barriers in these instances may necessitate the involvement of SLTs (Sekhon et al., 2015), a collaborative practice that is underrepresented in the literature reported in this scoping review. Existing research in the field of neurorehabilitation suggests that coworking is a productive way to engage people post-ABI as they work toward meaningful goals (Clarke & Forster, 2015). Similar principles could be applied, whereby family therapists and SLTs work together to deliver family therapy to PWCD.
Limitations and Future Research
The methodology used for this research was a scoping review, meaning that the study is limited in the evaluation of the quality of included papers. In addition, limiting the search to publications in the English language may have excluded other relevant literature. Research in the area of family therapy and ABI should purposively include PWCD, given the frequency of communication disability after brain injury. To achieve inclusion, communication-accessible research practices are required (Dee-Price et al., 2020; Jagoe et al., 2023; Luck & Rose, 2007; Shiggins et al., 2022). Future research should publish disaggregated data which includes reporting of the outcomes of interventions that are specific to PWCD. This transparency in outcomes could then be applied to clinical practice with PWCD. Establishing core outcome measures related to family therapy outcomes, including patient-reported outcome measures that are appropriate for PWCDs, is an important step that would allow a more robust comparison of studies and decisions about best practice in relation to family therapy and PWCD.
Conclusion
This scoping review has identified that a small evidence base exists for the use of family therapy after ABI. The studies included in this review demonstrated that people with ABI and their family members can benefit from family therapy. However, the paucity of research on the use of family therapy with PWCD after ABI, risks creating or perpetuating an inequality of evidence-based care, when compared with people with ABI without a communication disability. Research that is representative of PWCD is an imperative if equal access to interventions is to be achieved.
Appendices
Note. PWCD = people with a communication disability; PWA = people with aphasia; SLT = speech and language therapist; CPT = communication partner training; ABI = acquired brain injury; SLP = speech and language pathologist; HSCP = health and social care professional; TBI = traumatic brain injury.
Complexe Systémique: key points
From a systemic point of view, the article asks a simple and unsettling question: who is family therapy for when one member can no longer speak as before? Brain injury redistributes roles, parental, marital, sibling, and these roles are negotiated through talk. Yet half of the 24 studies reviewed exclude people with communication disabilities, most often de facto, because the setting assumes fluent verbal exchange. Therapy is then done about the person rather than with them, reproducing in the consulting room the exclusion the family already lives. The proposed way forward is concrete: team up with speech and language therapy, adapt materials, make the setting accessible rather than screening families out. The review remains descriptive, with no appraisal of study quality and heterogeneous measures. Read alongside the article on narrative therapy for couples after brain injury, and the study of chronic critical illness as a family affair.
Notes from the original
Declaration of conflicting interests. The author(s) declared no potential conflicts of interest with respect to the research, authorship, and/or publication of this article.
Funding. The first author received a monetary award, in the form of the Tavistock Trust for Aphasia Student Prize, for the dissertation on which the paper was based.
References
Arksey H., O’Malley L. (2005). Scoping studies: Towards a methodological framework. International Journal of Social Research Methodology, 8(1), 19–32. https://doi.org/10.1080/1364557032000119616
Baker C. S., Worrall L., Rose M., Ryan B. (2019). Stroke health professionals’ management of depression after post-stroke aphasia: A qualitative study. Disability and Rehabilitation, 43(2), 217–228. https://doi.org/10.1080/09638288.2019.1621394
Barrow R. (2008). Listening to the voice of living life with aphasia: Anne’s story. International Journal of Language & Communication Disorders, 43(Suppl. 1), 30–46. https://doi.org/10.1080/13682820701697947
Bellon M., Crocker R., Farnden J., Gardner J., Sando S., Peterson C. (2015). Family support needs following acquired brain injury across metropolitan and regional/remote South Australia. Brain Impairment, 16(2), 131–144. https://doi.org/10.1017/brimp.2015.17
Berg K., Isaksen J., Wallace S. J., Cruice M., Simmons-Mackie N., Worrall L. (2022). Establishing consensus on a definition of aphasia: An e-Delphi study of international aphasia researchers. Aphasiology, 36, 385–400. https://doi.org/10.1080/02687038.2020.1852003
Blom Johansson M., Carlsson M., ÖStberg P., Sonnander K. (2013). A multiple-case study of a family-oriented intervention practice in the early rehabilitation phase of persons with aphasia. Aphasiology, 27(2), 201–226. https://doi.org/10.1080/02687038.2012.744808
Borenstein P., Linell S., Währborg P. (1987). An innovative therapeutic program for aphasia patients and their relatives. Scandinavian Journal of Rehabilitation Medicine, 19(2), 51–56.
Butera-Prinzi F., Charles N., Story K. (2014). Narrative family therapy and group work for families living with acquired brain injury. Australian and New Zealand Journal of Family Therapy, 35(1), 81–99. https://doi.org/10.1002/anzf.1046
Butera-Prinzi F., Charles N., Story K. (2016). Holding resilience in trust: Working systemically with families following an acquired brain injury. Journal of Social Work in Disability & Rehabilitation, 15(3–4), 285–304. https://doi.org/10.1080/1536710x.2016.1220882
Cava M. J., Buelga S., Musitu G. (2014). Parental communication and life satisfaction in adolescence. The Spanish Journal of Psychology, 17, Article E98. https://doi.org/10.1017/sjp.2014.107
Charles N., Butera-Prinzi F., Perlesz A. (2007). Families living with acquired brain injury: A multiple family group experience. NeuroRehabilitation, 22(1), 61–76. https://doi.org/10.3233/nre-2007-22107
Clark M. S., Rubenach S., Winsor A. (2003). A randomized controlled trial of an education and counselling intervention for families after stroke. Clinical Rehabilitation, 17(7), 703–712. https://doi.org/10.1191/0269215503cr681oa
Clarke D., Forster A. (2015). Improving post-stroke recovery: The role of the multidisciplinary health care team. Journal of Multidisciplinary Healthcare, 8, 433–442. https://doi.org/10.2147/jmdh.s68764
Collins R. C., Kennedy M. C. (2008). Serving families who have served: Providing family therapy and support in interdisciplinary polytrauma rehabilitation. Journal of Clinical Psychology, 64(8), 993–1003. https://doi.org/10.1002/jclp.20515
Couchman G., McMahon G., Kelly A., Ponsford J. (2014). A new kind of normal: Qualitative accounts of multifamily group therapy for acquired brain injury. Neuropsychological Rehabilitation, 24(6), 809–832. https://doi.org/10.1080/09602011.2014.912957
Covidence. (2021). Covidence: Better systematic review management. https://www.covidence.org/
Daudt H. M., van Mossel C., Scott S. J. (2013). Enhancing the scoping study methodology: A large, inter-professional team’s experience with Arksey and O’Malley’s framework. BMC Medical Research Methodology, 13(1), Article 48. https://doi.org/10.1186/1471-2288-13-48
Dausch B. M., Saliman S. (2009). Use of family focused therapy in rehabilitation for veterans with traumatic brain injury. Rehabilitation Psychology, 54(3), 279–287. https://doi.org/10.1037/a0016809
Davis J., Tadros E. (2019). Using medical family therapy with parents of an adult child with traumatic brain injury. The American Journal of Family Therapy, 47(4), 261–274. https://doi.org/10.1080/01926187.2019.1640652
Dawes K., Carlino A., van den Berg M., Killington M. (2022). Life altering effects on children when a family member has an acquired brain injury; A qualitative exploration of child and family perceptions. Disability and Rehabilitation, 44, 282–290. https://doi.org/10.1080/09638288.2020.1766582
Dee-Price B.-J. M., Hallahan L., Nelson Bryen D., Watson J. M. (2020). Every voice counts: Exploring communication accessible research methods. Disability & Society, 36(2), 240–264. https://doi.org/10.1080/09687599.2020.1715924
Dooley S., Walshe M. (2020). Management of cognitive communication difficulties in dementia: A cross-sectional survey of speech & language therapists in Ireland. Dementia Network. http://dementianetwork.ie/management-cognitive-communication-difficulties-dementia-cross-sectional-survey-speech-language
Dunsmuir S., Clifford V., Took S. (2006). Collaboration between educational psychologists and speech and language therapists: Barriers and opportunities. Educational Psychology in Practice, 22(2), 125–140. https://doi.org/10.1080/02667360600668246
Epstein N. B., Baldwin L. M., Bishop D. S. (1983). The McMaster family assessment device. Journal of Marital and Family Therapy, 9(2), 171–180. https://doi.org/10.1111/j.1752-0606.1983.tb01497.x
Florian V., Katz S. (1991). The other victims of traumatic brain injury: Consequences for family members. Neuropsychology, 5(4), 267–279. https://doi.org/10.1037/0894-4105.5.4.267
Galvin K. M., Braithwaite D. O., Bylund C. L., Braithwaite D. (2016). Family communication: Cohesion and change (9th ed.). Routledge.
Glass T. A., Dym B., Greenberg S., Rintell D., Roesch C., Berkman L. F. (2000). Psychosocial intervention in stroke: Families in recovery from stroke trial (FIRST). American Journal of Orthopsychiatry, 70(2), 169–181. https://doi.org/10.1037/h0087746
Gough D., Davies P., Jamtvedt G., Langlois E. V., Littell J. H., Akl E. A., Masset E., Merlin T., Pullin A. S., Ritskes-Hoitinga M., Røttingen J., Sena E. S., Stewart R., Tovey D., White H., Yost J., Lund H., Grimshaw J. M. (2020). Evidence Synthesis International (ESI): Position statement. Systematic Reviews, 9(1), 155. https://doi.org/10.1186/s13643-020-01415-5
Hawksley R., Ludlow F., Buttimer H., Bloch S. (2017). Communication disorders in palliative care: Investigating the views, attitudes and beliefs of speech and language therapists. International Journal of Palliative Nursing, 23(11), 543–551. https://doi.org/10.12968/ijpn.2017.23.11.543
Hersh D., Israel M., Shiggins C. (2021). The ethics of patient and public involvement across the research process: Towards partnership with people with aphasia. Aphasiology. 1(1–26). https://doi.org/10.1080/02687038.2021.1896870
Hibbard M. R., Cantor J., Charatz H., Rosenthal R., Ashman T., Gundersen N., Ireland-Knight L., Gordon W., Avner J., Gartner A. (2002). Peer support in the community: Initial findings of a mentoring program for individuals with traumatic brain injury and their families. Journal of Head Trauma Rehabilitation, 17(2), 112–131. https://doi.org/10.1097/00001199-200204000-00004
Hodgson J. L., Lamson A. L., Mendenhall T. J., Tyndall L. (2014). Introduction to medical family therapy: Advanced applications. In Hodgson J., Lamson A., Mendenhall T., Crane D. R. (Eds.), Medical family therapy: Advanced applications (pp. 1–9). Springer. https://doi.org/10.1007/978-3-319-03482-9_1
Jagoe C., McDonald C., Rivas M., Groce N. (2021). Direct participation of people with communication disabilities in research on poverty and disabilities in low and middle income countries: A critical review. PLOS ONE, 16(10), Article e0258575. https://doi.org/10.1371/journal.pone.0258575
Jagoe C., O’Reilly C. F., James L. E., Khaled E., Alazzawi H., Enright T. (2023). Interpersonal violence experienced by people with communication disabilities in Iraq: Sustainable development goals 16 and 5. International Journal of Speech-Language Pathology, 25(1), 130–135. https://doi.org/10.1080/17549507.2022.2146193
Klonoff P. S. (2014). Psychotherapy for families after brain injury. Springer.
Klonoff P. S., Koberstein E. J. (2010). Family life. In Klonoff P. S. (Ed.), Psychotherapy after brain injury: Principles and techniques (pp. 150–170). Guilford Press.
Koren P. E., DeChillo N., Friesen B. J. (1992). Measuring empowerment in families whose children have emotional disabilities: A brief questionnaire. Rehabilitation Psychology, 37(4), 305–321. https://doi.org/10.1037/h0079106
Kreutzer J. S., Kolakowsky-Hayner S. A., Demm S. R., Meade M. A. (2002). A structured approach to family intervention after brain injury. Journal of Head Trauma Rehabilitation, 17(4), 349–367. https://doi.org/10.1097/00001199-200208000-00008
Kreutzer J. S., Stejskal T. M., Godwin E. E., Powell V. D., Arango-Lasprilla J. C. (2010). A mixed methods evaluation of the Brain Injury Family Intervention. NeuroRehabilitation, 27(1), 19–29. https://doi.org/10.3233/nre-2010-0578
Larøi F. (2003). The family systems approach to treating families of persons with brain injury: A potential collaboration between family therapist and brain injury professional. Brain Injury, 17(2), 175–187. https://doi.org/10.1080/0269905021000010140
Lauer-listhaus B. (1991). Group psychotherapy for families of head injured adults: A psychoeducational approach. Counselling Psychology Quarterly, 4(4), 351–354. https://doi.org/10.1080/09515079108254443
Levac D., Colquhoun H., O’Brien K. K. (2010). Scoping studies: Advancing the methodology. Implementation Science, 5(1), 69. https://doi.org/10.1186/1748-5908-5-69
Levin K. A., Dallago L., Currie C. (2012). The association between adolescent life satisfaction, family structure, family affluence and gender differences in parent–child communication. Social Indicators Research, 106(2), 287–305. https://doi.org/10.1007/s11205-011-9804-y
Luck A. M., Rose M. L. (2007). Interviewing people with aphasia: Insights into method adjustments from a pilot study. Aphasiology, 21(2), 208–224. https://doi.org/10.1080/02687030601065470
Maitz E. A., Sachs P. R. (1995). Treating families of individuals with traumatic brain injury from a family systems perspective. Journal of Head Trauma Rehabilitation, 10(2), 1–11. https://doi.org/10.1097/00001199-199504000-00003
Manning M., MacFarlane A., Hickey A., Galvin R., Franklin S. (2021). “I hated being ghosted”: The relevance of social participation for living well with post-stroke aphasia: Qualitative interviews with working aged adults. Health Expectations, 24(4), 1504–1515. https://doi.org/10.1111/hex.13291
Marlowe D. (2011). Bridging conversations: Discussing the intra-professional relationship between medical family therapy and family therapy. Journal of Family Therapy, 35(2), 119–138. https://doi.org/10.1111/j.1467-6427.2011.00553.x
Mays N., Roberts E., Popay J. (2001). Synthesising research evidence. In Fulop N., Allen P., Clarke A., Black N. (Eds.), Studying the organisation and delivery of health services: Research methods (pp. 188–220). Routledge.
McDermott G. L., McDonnell A. M. (2013). Acquired brain injury services in the Republic of Ireland: Experiences and perceptions of families and professionals. Brain Injury, 28(1), 81–91. https://doi.org/10.3109/02699052.2013.857790
Moos R. H., Moos B. S. (1981). Family environment scale manual. Consulting Psychologists Press.
Nichols F., Varchevker A., Pring T. (1996). Working with people with aphasia and their families: An exploration of the use of family therapy techniques. Aphasiology, 10(8), 767–781. https://doi.org/10.1080/02687039608248449
Olson D. H., Gorall D. M. (2003). Circumplex model of marital and family systems. In Walsh F. (Ed.), Normal family processes: Growing diversity and complexity (pp. 514–548). The Guilford Press.
Perlesz A., OʼLoughlan M. (1998). Changes in stress and burden in families seeking therapy following traumatic brain injury. International Journal of Rehabilitation Research, 21(4), 339–354. https://doi.org/10.1097/00004356-199812000-00001
Perlick D. A., Straits-Troster K., Strauss J. L., Norell D., Tupler L. A., Levine B., Luo X., Holman C., Marcus T., Dixon L. B., Dyck D. G. (2013). Implementation of multifamily group treatment for veterans with traumatic brain injury. Psychiatric Services, 64(6), 534–540. https://doi.org/10.1176/appi.ps.001622012
Rolland J. S., Walsh F. (2005). Systemic training for healthcare professionals: The Chicago Center for Family Health approach. Family Process, 44(3), 283–301. https://doi.org/10.1111/j.1545-5300.2005.00060.x
Romero-Abrio A., Martínez-Ferrer B., Musitu-Ferrer D., León-Moreno C., Villarreal-González M. E., Callejas-Jerónimo J. E. (2019). Family communication problems, psychosocial adjustment and cyberbullying. International Journal of Environmental Research and Public Health, 16(13), 2417. https://doi.org/10.3390/ijerph16132417
Rosenthal M., Young T. (1988). Effective family intervention after traumatic brain injury: Theory and practice. Journal of Head Trauma Rehabilitation, 3(4), 42–50. https://doi.org/10.1097/00001199-198812000-00007
Sekhon J. K., Douglas J., Rose M. (2015). Current Australian speech-language pathology practice in addressing psychological well-being in people with aphasia after stroke. International Journal of Speech-Language Pathology, 17(3), 252–262. https://doi.org/10.3109/17549507.2015.1024170
Shiggins C., Ryan B., O’Halloran R., Power E., Bernhardt J., Lindley R. I., McGurk G., Hankey G. J., Rose M. L. (2022). Towards the consistent inclusion of people with aphasia in stroke research irrespective of discipline. Archives of Physical Medicine and Rehabilitation, 103(11), 2256–2263. https://doi.org/10.1016/j.apmr.2022.07.004
Smith-Acuña S. (2010). Systems theory in action: Applications to individual, couple, and family therapy. Wiley.
Söderström S., Fogelsjöö A., Fugl-Meyer K. S., Stenson S. (1992). Traumatic brain injury crisis intervention and family therapy—management and outcome. Scandinavian Journal of Rehabilitation Medicine, 26(1), 132–141.
Stead A., White J. H. (2019). Loss of intimacy. A cost of caregiving in aphasia. Topics in Language Disorders, 39(1), 55–70. https://doi.org/10.1097/tld.0000000000000175
Straits-Troster K., Gierisch J. M., Strauss J. L., Dyck D. G., Dixon L. B., Norell D., Perlick D. A. (2013). Multifamily group treatment for veterans with traumatic brain injury: What is the value to participants? Psychiatric Services, 64(6), 541–546. https://doi.org/10.1176/appi.ps.001632012
Todd J., Satz P. (1980). The effects of long-term verbal memory deficits: A case study of an adolescent and his family. Journal of Marital and Family Therapy, 6(4), 431–438. https://doi.org/10.1111/j.1752-0606.1980.tb01336.x
Townend E., Brady M., McLaughlan K. (2007). Exclusion and inclusion criteria for people with aphasia in studies of depression after stroke: A systematic review and future recommendations. Neuroepidemiology, 29(1–2), 1–17. https://doi.org/10.1159/000108913
Tricco A. C., Lillie E., Zarin W., O’Brien K. K., Colquhoun H., Levac D., Moher D., Peters M. D., Horsley T., Weeks L., Hempel S., Akl E. A., Chang C., McGowan J., Stewart L., Hartling L., Aldcroft A., Wilson M. G., Garritty C.,. . .Straus S. E. (2018). PRISMA extension for Scoping Reviews (PRISMA-ScR): Checklist and explanation. Annals of Internal Medicine, 169(7), 467–473. https://doi.org/10.7326/m18-0850
Turnblom M., Myers J. S. (1952). A group discussion program with the families of aphasic patients. Journal of Speech and Hearing Disorders, 17(4), 393–396. https://doi.org/10.1044/jshd.1704.393
Tyndall L., Hodgson J. L., Lamson A. L., White M. D., Knight S. M. (2012). Medical family therapy: Charting a course in competencies. Contemporary Family Therapy, 34(2), 171–186. https://doi.org/10.1007/s10591-012-9191-9
Walker S., Akister J. (2004). Applying family therapy: A guide for caring professionals in the community. Russell House Publishing.
Washington Group on Disability Statistics. (2016). Short set of disability questions. http://www.washingtongroup-disability.com/washingtongroupquestion-sets/short-set-of-disability-questions
Watzlawick P., Coyne J. C. (1980). Depression following stroke: Brief, problem-focused family treatment. Family Process, 19(1), 13–18. https://doi.org/10.1111/j.1545-5300.1980.00013.x
Yeates G. N., Luckie M., de Beer Z., Khela P. (2010). Elucidating the psychosocial context of “post-concussion syndrome” (PCS): A case study from post-Milan systemic family therapy. Journal of Family Therapy, 32(2), 186–202. https://doi.org/10.1111/j.1467-6427.2010.00493.x
Zarski J. J., West J. D., DePompei R., Hall D. E. (1988). Chronic illness: Stressors, the adjustment process, and family-focused interventions. Journal of Mental Health Counselling, 10(2), 145–158.
Reformatted republication of Family Therapy as an Intervention for Adults With Aphasia and Other Communication Disabilities After Acquired Brain Injury: A Scoping Review, by Jessica Henihan, Rebecca Henihan and Caroline Jagoe, Rehabilitation Counseling Bulletin, vol. 68, no 3 (2025), doi: 10.1177/00343552241236859, under a CC BY 4.0 licence. Edition and layout: Complexe Systémique, September 2026 — the work has been modified under the terms of the licence (layout adapted). Neither the authors nor the publisher are responsible for this edition; the original version prevails.
This is the original article “Family Therapy as an Intervention for Adults With Aphasia and Other Communication Disabilities After Acquired Brain Injury: A Scoping Review”, published in Rehabilitation Counseling Bulletin (2025) under a CC BY 4.0 licence. Republished by Complexe Systémique: the author’s text is unchanged; only the presentation has been adapted for reading online, as set out at the head of this page.
Read the original articleHow to cite this article
Henihan, J., Henihan, R., et Jagoe, C. (2025). Family Therapy as an Intervention for Adults With Aphasia and Other Communication Disabilities After Acquired Brain Injury: A Scoping Review. Complexe Systémique. https://app.complexe-systemique.com/en_GB/articles/family-therapy-as-an-intervention-for-adults-with-aphasia-and-other-communication (Original work published in 2024 in Rehabilitation Counseling Bulletin, 68(3), 182-196 (2025); republished in 2025 by Rehabilitation Counseling Bulletin, https://journals.sagepub.com/doi/10.1177/00343552241236859)
To go further
- La thérapie narrative de couple face aux récits de discontinuité après une lésion cérébraleCouples after brain injury.
- Quand la maladie critique chronique est une affaire de famille : une étude qualitative à perspectives multiples sur l’implication des familles dans les soins de longue duréeIllness as a family affair.
- Les jeunes adultes et leur famille face à la maladie mentale : l’utilité des conversations de soutien centrées sur la famille en santé mentale communautaireFamily-centred conversations.
Related training courses
 Symposium
État des Lieux: a psychological approach to spaces
Replay of the “État des Lieux” conference (Paris, 16 October 2026): Ivy Daure, Maurizio Frisina, Viola Sallay and Gilbert Pregno on places as a clinical resource. In French.
 Certifying course
Training in Systemic Therapy and Interventions – Cycle 1
Certifying training cycle in systemic therapy and interventions – year 1. Courses, supervision and practice, aligned with EFTA/SFTF. In French.
 Certifying course
Training in Systemic Therapy and Interventions – Cycle 2
Certifying training cycle in systemic therapy and interventions – year 2. Clinical complexity, supervision and practice. EFTA/SFTF aligned. In French.
 Certifying course
Training in Systemic Therapy and Interventions – Cycle 3
Certifying training cycle in systemic therapy and interventions – year 3. In-depth intervention, supervision and practice. EFTA/SFTF aligned. In French.
Related articles
 Blog
Adult parentification: when being useful becomes a condition for being loved
Why is it sometimes so hard to hand over? Julien Besse explores parentification and parentalisation, acknowledgement and the place we take in our adult relationships.
 Scientific
Digital Co-Regulation and Dysregulation in Romantic Relationships: A Systemic Model of Technology-Mediated Emotional Processes
Checking, chasing, blocking: 31 interviews show how the phone regulates or dysregulates a couple’s anxiety, with a systemic model of the loop.
 Scientific
Transitioning to the Business of a Session in Collaborative-Dialogic Meetings: A Conversation Analysis
How do Open Dialogue therapists move to the business of a session? The open question creates silences and family negotiation: a conversation analysis of ten sessions.
 Scientific
“One Can Have All Sorts of Good Intentions but Sometimes in Everyday Life, It Turns Out Differently”: Change Agreements in Couples' Everyday Lives
Six Danish couples followed after an online couple program: their change agreements become guilt-inducing contracts, shared understanding or revealers of inequality.