Adoption & Fostering · Child protection
Interrupting a cycle of placement instability with short-term residential care: Trauma-informed family-like relational practice in one specialist unit
When placement breakdowns pile up, each failure makes the next more likely. In Northern Ireland, a small house takes in children under 12 for a few months to break this cycle, with an openly stated rule: love them. Of 34 trajectories, most children moved on to foster care, and staff describe what, day to day, makes this place both family-like and trauma-informed.
This is a reformatted republication of Interrupting a cycle of placement instability with short-term residential care: Trauma-informed family-like relational practice in one specialist unit, by Mandi MacDonald and Kathryn Gillespie, published in Adoption & Fostering (SAGE) (2023), doi: 10.1177/03085759231212499, under a CC BY 4.0 licence. Prepared by Complexe Systémique in September 2026: the authors’ text is unchanged; the layout has been adapted for reading online, which constitutes a modification of the work under the terms of the licence. The note to Table 1 is grouped in the notes; the biographies and supplementary material are not reproduced. This edition was made neither by the authors nor by the publisher, who are not responsible for its content or for any errors. The original version prevails.
While children’s safety is paramount, risk-aversion is unhelpful if staff feel afraid to engage in meaningful relationship-building.
Mandi MacDonald and Kathryn Gillespie
Abstract
Continuous caring relationships are crucial to the wellbeing of children living in out-of-home care, with the family environment of long-term foster care usually the preferred placement for achieving relational permanence. Some children, however, experience a cycle of instability with the impact of placement disruption exacerbating emotional and behavioural difficulties and thereby undermining subsequent foster relationships. This paper reports on a service evaluation of a residential facility specialising in short-term placements for children who have experienced disruption, with the aim of interrupting the cycle of placement instability. Overview of 34 children’s placement trajectories show that most were enabled to re-enter foster care and of those who are now aged over 18 years (n = 29), over half (n = 16) remained in family placements until adulthood. For four children, detailed individualised assessment indicated residential care as the most appropriate option for avoiding future disruption. The paper gives cause for optimism that relationships in the residential setting have the potential to build emotional resilience and capacity for connection. There is paucity of information on how residential staff achieve these relationships in practice. Focus groups and interviews with ten staff and managers illuminate relational practices in the residential setting that are simultaneously family-like and trauma-informed.
Keywords: Children in care, Children’s House, disruption, residential unit, trauma-informed care, short-term placements
Introduction
The United Nations Convention on the Rights of the Child enshrines children’s right to a safe and supportive environment in which to grow up (United Nations, 1989). As the primary site for childrearing, the centrality of the family is evident across diverse cultures (Trask, 2009; Welch, 2018; Gwenzi, 2020). Reflective of this, when children experience maltreatment and need alternative out-of-home care, a ‘family or family-like environment’ such as foster care (Strijbosch et al., 2015: 209) is generally favoured over group residential care for supporting social and emotional development (Dozier et al., 2014).
Stable foster care placements can afford the continuous caring relationships that are fundamental to securing better outcomes for care-experienced youth throughout their childhood and into adult life (Boddy, 2013). A strong supportive social network can contribute to resilience (Tahkola et al., 2021) and avoid the negative social, emotional and health outcomes associated with isolation (Gypen et al., 2017), especially during significant life transitions (Samuels and Pryce, 2008).
Some children, however, struggle to adapt to foster family life. Many are affected by trauma and have developed unhelpful coping strategies, which can undermine placement stability and relationships with foster carers (Oosterman et al., 2007; Jakobsen, 2013; Strijbosch et al., 2015). Past experiences of maltreatment impact internal working models and impede children’s capacity for attachment and interpersonal connection (Ainsworth et al., 1978; Bowlby, 1988; Schofield and Beek, 2018; Tahkola et al., 2021), leading to them developing a preference for self-reliance (Samuels and Pryce, 2008) and reluctance to seek help or new connections (Blakeslee and Best, 2019; Okpych and Gray, 2021). Placement disruption can further exacerbate emotional and behavioural difficulties, contributing to a cycle of instability (James et al., 2004; Rubin et al., 2004; Hussey and Guo, 2005). While long-term placement stability is a goal for all children, those who have experienced multiple foster placement disruption, or who have complex needs, can benefit from short-term placement in a residential setting (What Works Centre for Children’s Social Care, 2019; Burbidge, Keenan and Parry, 2020), often with the aim of preparation for further long-term placement (Hart, LaValle and Holmes, 2015).
Because residential care is often viewed as a placement of last resort, those children who are cared for in specialist short-term group settings typically have high intensity needs that foster care or community services have been unable to meet (Gilligan, 2014). Children in such settings, including those with a history of multiple disruption, typically have complex mental health and behavioural difficulties. They require a period of stability in their living arrangements and help to recover from adversity and build healthy attachment relationships (Ainsworth and Hansen, 2015). Various working approaches have been developed for residential settings and, to varying extents, assessed (Weisz et al., 2013; Strijbosch et al., 2015). These often focus on strengthening carer–child relationships (Neimetz, 2011; Garcia Quiroga and Hamilton-Giachritsis, 2017) and promoting secure attachment (Burbidge, Keenan and Parry, 2020). Because of the prevalence of adversity and maltreatment, children need a stable nurturing environment, close trusting relationships (Huefner and Ainsworth, 2021), and trauma-sensitive caregiving to promote growth and recovery (Hart, LaValle and Holmes, 2015).
At the same time, specialist residential settings should aim to align everyday practice to principles of care rather than meticulously implementing a programme or care curriculum (Gilligan, 2014). Huefner and Ainsworth (2021) emphasise the importance of a caregiving environment that maximises the potential of all day-to-day interactions to achieve a beneficial emotional and behavioural experience. A trauma-informed caregiving milieu is one where care is predictable, dependable, and ordered, enabling children to feel worthwhile and have their specific needs taken care of, leading to improved functioning for children and young people with emotional and behavioural challenges (Huefner and Ainsworth, 2021). Since children who have been let down or harmed may have little capacity to connect with helping adults, such relational caring practices need to be purposefully undertaken by staff who are skilled, competent and empowered (Smart and Thorpe, 2020).
Foster care is often considered preferable to group care, partly because, in the ‘normality’ of the family context, children’s relationships with foster carers are presumed to be fundamentally different from those with residential staff who may be experiencing tension between their professional and parental roles (Fowler, 2016) in the more ‘institutional’ setting (Kendrick, 2013: 77). Some have noted a prevailing culture of risk aversion and associated fear, which shapes the daily practice of residential childcare workers, stifling expressions of warmth and affection (Brown, Winter and Carr, 2018) and creating professional distance and ambivalence (Kendrick, 2013), causing some staff to eschew affection, physical contact or emotional depth in favour of a neutral professional approach (Brown, Winter and Carr, 2018).
However, other research has explored how the residential group care setting (which is both a home and a place of work) can be family-like (Lone and Paulsen, 2018; Gwenzi, 2020). A different kind of family experience, albeit distinctive and different from other family forms, can be achieved (Smart and Thorpe, 2020); some young people use a metaphor of family to describe positive experiences of residential care, articulating the family-like nature of these relationships in terms of ‘being there’ and ‘caring’ (Kendrick, 2013: 82). Some children and young people have described care as resembling family life, or staff resembling parents, with certain practices, for example, around mealtime routines, offering family-like experiences (Punch et al., 2009; McIntosh et al., 2011; Kendrick, 2013). Within the 24/7 milieu of life and mundane care, small but significant micro-interactions can lay a foundation of trust, connection and optimism. What matters to young people are seemingly small gestures that validate their personal significance, and convey that staff know, and want to know them, seeing the individual beneath the behaviour (Smart and Thorpe, 2020). Kindness, compassion and love, which are often taken for granted as features of family life, also can be viewed as professional values that facilitate relational connection and emotional safety for children in residential settings (Smart and Thorpe, 2020).
While placement moves should be avoided (Strijbosch et al., 2015), purposeful short-term residential options can be a turning point in children’s placement trajectories (Havlicek, Garcia and Smith, 2013), with the potential to interrupt a cycle of placement instability. Relationships formed with residential staff can enable children to trust, feel safe and make use of adult support, revising their internal models of adult–child relationships and providing opportunities to develop strategies for emotional regulation and problem-solving (Huefner and Ainsworth, 2021). The hope is that the benefits gained from these short-term but positive relational experiences will enable children to benefit from long-term placement and lay a foundation upon which stability might be achieved.
There is a paucity of research that explores the perspectives of residential staff regarding caregiving relationships (Brown, Winter and Carr, 2018), or how they help children to develop and maintain relational capacities (Samuels and Pryce, 2008). While the importance of trauma-informed care in the residential setting is well established, little is known about what this looks like in everyday practice (Johnson, 2017). This paper aims to illuminate effective day-to-day caregiving by describing trauma-informed, family-like relational practices in one short-term residential unit which aims to interrupt a cycle of instability for children with complex needs who have experienced placement disruption, preparing them for long-term family placement.
Children’s House: Purpose And Approach
Children’s House is a small facility that specialises in providing temporary residential placements for up to four children aged under 12 years who have experienced multiple placement breakdown. The unit aims to interrupt the cycle of instability by providing a safe, stable environment and period away from family placements, with the pre-adolescence stage considered a ‘window of opportunity’ to build relational skills and prepare children for a further opportunity for long-term placement.
Care within Children’s House is underpinned by the principles of Dyadic Developmental Psychotherapy (DDP) (Becker-Weidman and Hughes, 2008; Hughes, Golding and Hudson, 2015) which views the caregiver–child relationship as a platform for recovery when children exhibit symptoms of emotional or attachment disorders, and/or complex trauma. DDP equips caregivers with trauma-informed parenting approaches to provide a relational environment that supports children’s emotional regulation, connection and security. Patterns of caregiving and communication within the Children’s House create a milieu that promotes recovery and enables the development of trusting, supportive relationships. A key element of DDP is the PACE (Playfulness, Acceptance, Curiosity, Empathy) approach to parenting. This teaches carers to seek to understand and respond calmly to challenging behaviours. The limited research suggests some improvement in children’s emotional, behavioural and attachment-related difficulties (Becker-Weidman, 2006; Hughes, Golding and Hudson, 2015) and parental reports of improved relationships, understanding children’s needs, and ability to support co-regulation (Wingfield and Gurney-Smith, 2019).
Children’s House also utilises the Narrative Model (Coman et al., 2016; McGill et al. 2018), recognising that some children do not understand why they are in care and fill knowledge gaps with self-blaming myths, affecting their self-worth and relationships. The model aims to help children placed in care to adjust psychologically to their new circumstances, enabling the re-conceptualisation of relationships with birth families, and strengthening placement stability by supporting children in understanding and accepting their situation.
A further distinctive aspect of the unit’s approach is an integrated delivery model with Barnardo’s fostering service, supporting children’s transitions from residential care to family placements (where appropriate). This is achieved by regular meetings between staff and managers in both services, co-working assessment and planning, and joint training. Short-break foster placements facilitate the assessment of each child’s fostering support needs and functioning in a family setting.
Method
This paper reports staff perceptions of approaches to day-to-day care within Children’s House, focusing on how caregiving is both family-like and trauma-informed. Themes are drawn from focus groups and individual interviews with staff (4 individuals) and managers (6 individuals), conducted as part of a service evaluation. Research conducted by the authors (MacDonald and Marshall, 2021) with the associated Barnardo’s fostering service found that several children with histories of multiple placement disruption and complex needs had subsequently experienced relational permanence with their foster carers (McSherry and Fargas Malet, 2018) after leaving Children’s House. Barnardo’s invited the authors to undertake a service evaluation with a view to identifying good practice in Children’s House that might contribute to this desired outcome, and to pinpoint areas for improvement. This focused on understanding the purpose of Children’s House, and the team’s distinctive working practices and approaches. Informed consent was given for focus groups and interviews which were audio-recorded, transcribed and checked by researchers for accuracy. Transcripts were analysed manually following the principles of thematic analysis (Braun and Clarke, 2006). Anonymised administrative records provided an overview of 34 children’s placement trajectories (2003–2020). Information obtained included: number of placement moves prior to Children’s House; length of time resident in Children’s House; type and duration of subsequent placement; and subsequent placement disruption – and children’s ages at each stage. No file recordings or identifying information were accessed for any of the children.
Children’s Placement Journeys
Table 1 summarises placement timelines for children placed in Children’s House between 2003 and 2020, indicating age at first entry to care, age of entry to Children’s House, length of time spent there and type of subsequent placement. Children entered the unit aged between five and ten years (mean: 8), having experienced between two and 26 placement moves (mean: 7). Children spent between four and 40 months in Children’s House (mean: 25). They were aged seven to 12 years when they left (mean: 10).
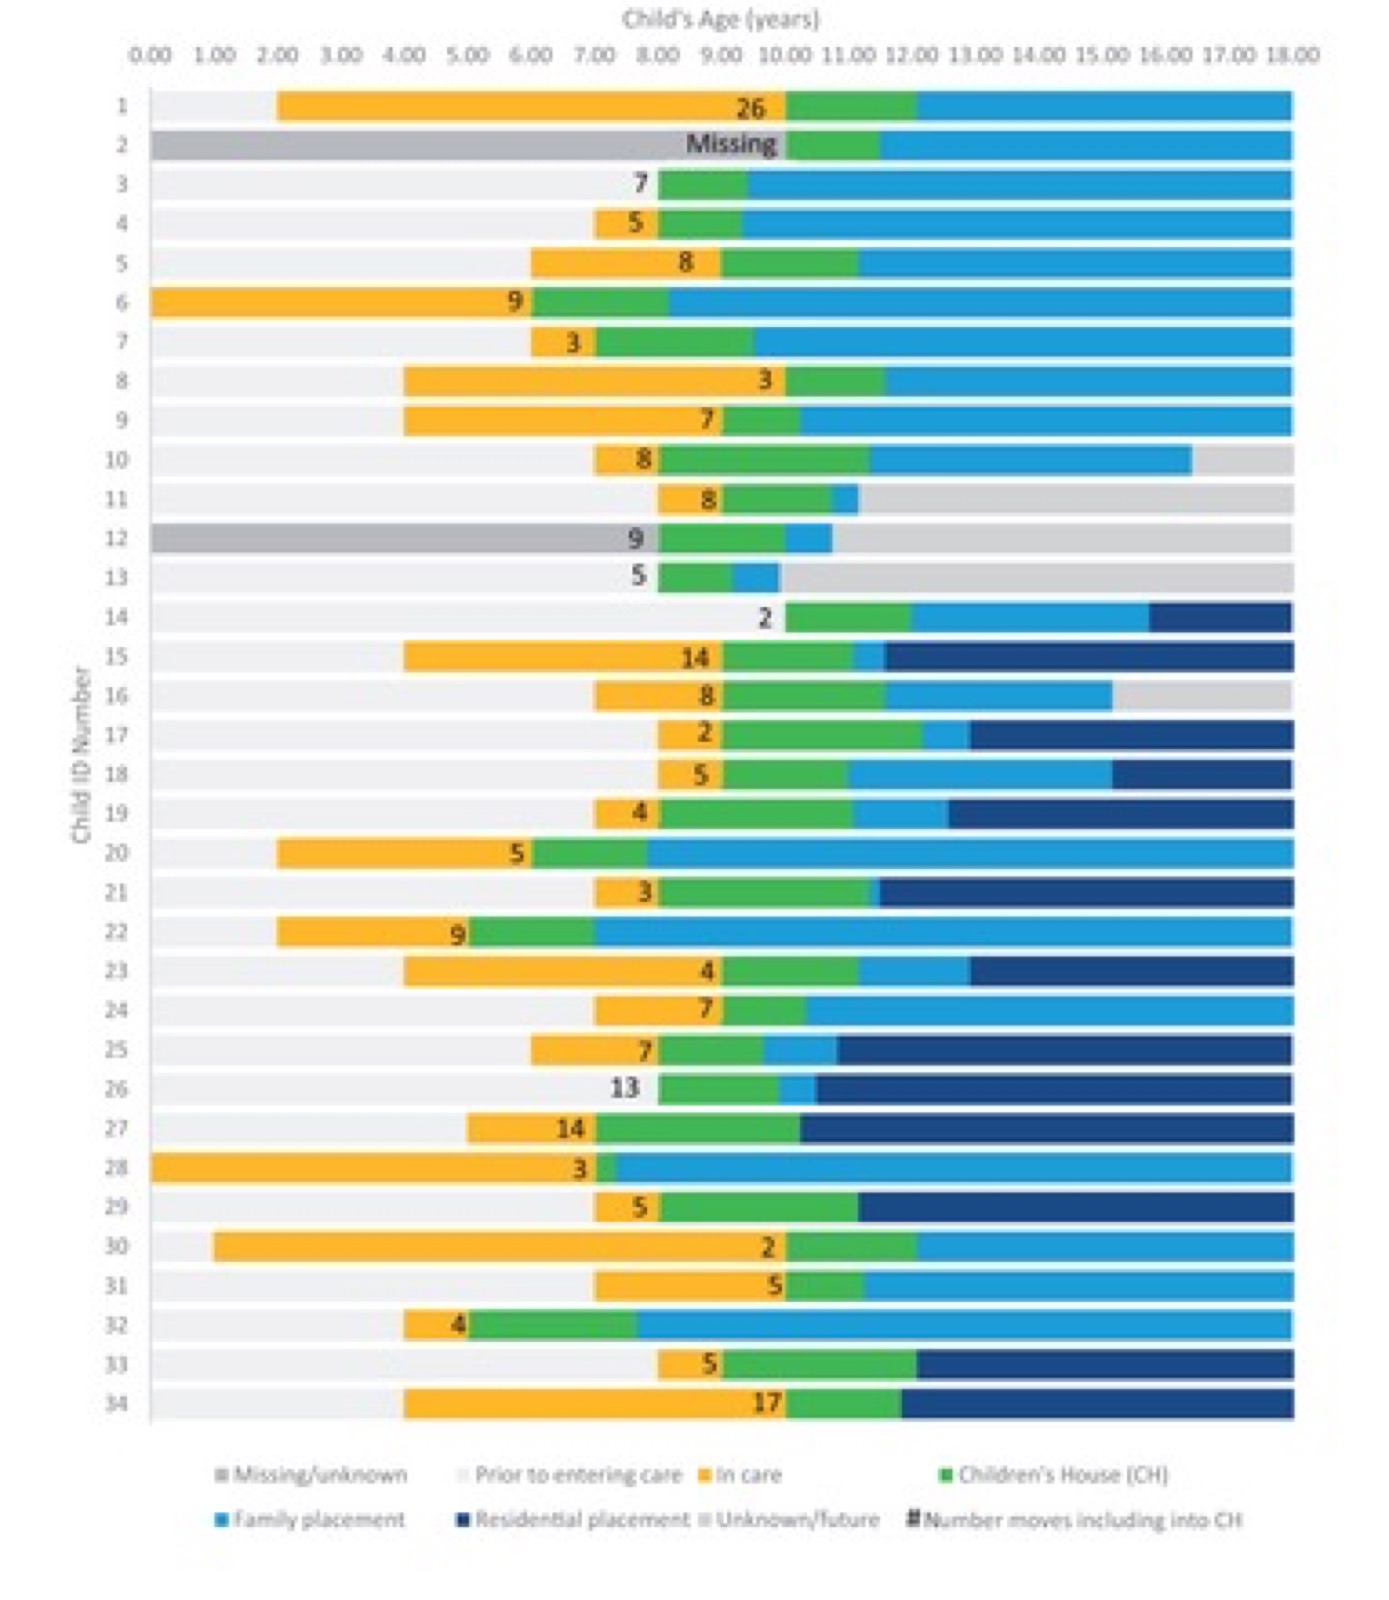
Four children moved directly to a long-term residential placement after Children’s House (one of these was in a hospital setting). All other children (n = 30) moved to a family placement: Barnardo’s foster carers (n = 27), other agency foster carers (n = 1), kinship foster carers (n = 2), or adoption (n = 1). Of these, over half (n = 16) remained in family placements until adulthood. Five more children were still in their family placement at the time of writing. Two remained several years in their foster placement until the age of 15 and 16 years and were known to have ongoing close relationships with their foster family. Seven children moved to foster placements for short periods of time before returning to residential settings.
Among those reaching adulthood in family placements, the mean placement length in Children’s House was 21.3 months. Those who entered residential placements after a disrupted family placement had a mean Children’s House placement length of 25 months, and those who entered residential placements directly from Children’s House had a mean placement of 26.5 months.
Family-Like Trauma-Informed Relationships In The Residential Setting
Love And Trust
There was consensus from managers and staff of a conscious focus on creating a close approximation to loving, supportive family life. Building relationships with the children was considered to be a natural and crucial aspect of working in Children’s House, with foundations established prior to the child’s arrival. They described the introduction and arrival process: beforehand, children receive letters and photographs from staff, welcoming them to their new home, and emphasising that ‘we’re excited for them to come and live with us’ (Manager). Reassurance that staff had experience caring for many children was considered to help children begin to feel safe.
Relationships included displays of affection which some staff viewed as being similar to how they would treat their own children:
I wouldn’t have tucked my own children into bed at night without a wee hug and saying in the morning, ‘love you’. So, I do exactly the same thing with the children in Children’s House and I’m glad to say a few of them now have got to the stage where they’ll say it back to me. (Staff)
While it was not expected that children would form relationships with all staff, there was optimism that they would with some, encouraged by natural ‘chemistry’ (Staff). Building positive bonds and memories with staff members was a key part of Children’s House life, including a cleaner and handyman who ‘also are very much a part of it’ (Manager).
Staff described building children’s trust and confidence that ‘adults are capable of keeping them safe’. Opportunities for children to feel loved and lovable were considered crucial, and staff described providing verbal assurance to affirm this:
So often we hear them saying to us, ‘But sure, who would love me?’ When we’re telling them 20 times a day, ‘Well, I do actually,’ but they find that very hard to accept because of their past.
Staff observed that complex attachments often shaped relationships with children, who sometimes experienced competing loyalties. Staff described supporting them during difficult processes of accepting that they would not be returning to their birth parents, and when birth families did not maintain contact:
As harsh as it is, it’s when the family don’t send birthday cards, don’t send Christmas cards and don't attend contact, that’s when kids start to realise. But then it's also providing that emotional support to them when that doesn't happen.
A related objective was building ‘transferable’ relationships (Staff) that would enable children to build relationships in their next placements. Experiencing loving relationships was seen as fundamental to children’s future ability to replicate this, with staff anticipating the gains for children’s adult futures.
Genuineness was considered beneficial in developing relationships with children, who managers felt could sense this. Staff reported that being prepared to provide a nurturing and loving environment was crucial:
If you don’t want to come in here and wear your heart on your sleeve and absolutely just love these children, there’s no point in coming here because you’re not going to do them any good.
Managers and staff reflected that this approach was not for everyone, ‘not every residential social worker is comfortable with providing that kind of care to young children’, and required reflection, team support and awareness around boundaries that differed from other residential settings. Staff noted the importance of working reflectively, regularly asking themselves whether they had done ‘the right thing’, and that discussion strengthened their practice.
Practices Of Family And Home
In addition to building transferable, family-like relationships, there was a sense from managers and staff of attempts to provide an environment resembling ‘ordinary’ family life (Manager). Staff expressed a desire for normality within children’s lives, noting that lacking a typical family life made them ‘feel different all the time’:
It doesn't feel like a residential facility. Just feels like a proper home and that's what we strive to make it feel like.
I think that’s probably one of the things […] the team do really well. The ordinariness, […] a family life within the residential life. (Manager)
That Children’s House was a child’s home, albeit temporary, was reinforced in ways including personalised decoration and photographs, and family-style routines around mealtimes and play, which enhanced the wider environment of care, nurturing and relationship-building:
His overriding memory of Children’s House was the cook’s spaghetti bolognese, and he says when he thinks of that, it brings him back to this really warm and nurturing time in his life. (Manager)
Managers acknowledged challenges associated with providing this environment alongside different children’s needs but reiterated that often day-to-day life resembled ‘very basic family routines’. However, managers and staff also reported that approaches were shaped by trauma-awareness of, for example, challenges surrounding transitions:
Going upstairs to downstairs is a transition […]. Sometimes it’s that absolute, thrown back to living at home and not knowing what they were going to see. […] So, our staff are just reminded […] every time that child is doing anything different, it’s a lot harder for them. (Manager)
There were challenges associated with providing a family-like atmosphere for ‘traumatised’ children, including safety. For example, children often had to be separated:
It breaks my heart that sometimes, well, quite often, we don't get to do your sort of normal family dinnertime routine. […] But unfortunately, safety has to come first, and typical, a day like Christmas. […] They were so excited, which can lead to all sorts of things going wrong. So, we made the staff decision that it was best to let them have a little bit of time together in the morning and then get them all off separated. (Staff)
Emotional Co-Regulation
Offering an environment and processes that enabled staff to come alongside children in a process of emotional co-regulation was crucial. For example, arrival is calm, controlled, and intentional. Before moving in, a child will see the Children’s House without other children present, and then have progressively longer visits and stays at a flexible pace:
Children’s histories are often around a panicked move and we’re trying to say, ‘No. We do this in a considered way. We’re looking forward to having you come to live here and there is no panic.’ The adults are actually in control. (Manager)
Staff reported attempting to maintain stability during transitions into Children’s House by encouraging the continuation of hobbies, and where possible, staying on at the same school. Education was a high priority and additional steps were taken over Covid-19 lockdowns to ensure access to continued provision. Providing this period of stability, continuity and security was seen as crucial after multiple moves. Managers highlighted demonstrating calmness and control in meeting children’s needs, where in the past, adults may have been unable to cope:
Quite often they’re presented to us as children where the adults have no clue what to do with them. […] [We can] say, ‘No. Well, hang on, we can take this control back,’ and say, ‘There are adults in your life now who absolutely can care for you and meet your needs.’ (Manager)
Stability towards difficult behaviours was also communicated to children, who previously may have attempted to achieve a sense of control through behaviours undermining placement stability:
[Those behaviours] are not okay. We talk all of those things through, but you’re still gonna be living here. […] it doesn’t change because of that one thing. (Manager)
Emotionally, relationships involved building up self-worth, including through responsiveness to feelings and activities that helped children feel good about themselves. Staff and managers discussed how a lack of positive coping mechanisms had contributed to previous placement breakdowns and highlighted the importance of empathy and acceptance in helping children to recognise emotions and find healthier ways of coping:
Acknowledging that it’s okay to feel the way that they feel. It’s just not okay to behave in that way about that feeling. […] The coping mechanisms those children get living in Children’s House, that follow them into placement, really are what helps make those placements thereafter become more stable for those children. (Manager)
Staff and managers described trauma-informed approaches towards challenging behaviours, including demonstrating acceptance and the ability to handle these, and providing ‘safety and a controlled environment’ for co-regulation.
Curiosity And Acceptance
Managers reported that multiple moves meant that ‘very often nobody has really got to know this child terribly well’. At Children’s House, emphasis was placed on curiosity in getting to know each child, and acceptance of their background:
We knew their story and we still wanted them to come so, so there’s something very reassuring to children […] that we are able to start very early on about being curious about them and about their lives and what they like. (Manager)
Staff noted benefits to getting to know children, including improved knowledge of needs, both within Children’s House and for future placements, and offering children the opportunity to experiment and identify their own interests.
Curiosity was also applied within narrative work, which focused on children’s past, present and future, and is used with young people to improve understanding of their histories and biological family and allowing them to consider ‘what their place may be in a future fostering family’ (Staff):
Unpack some of those past experiences to look up the reasons for those placement disruptions, to look at the past experience of family life with a view to preparing them for a future foster placement. (Manager)
Language in records reflected acceptance by describing adults’ responsibility to meet children’s needs, rather than for children to change their behaviour:
I read files that very much placed the onus of what happened with the child. […] And children understand […] they were being held responsible for the decisions that were made around them, and if only they behaved better, if only they had done differently. And actually, that's not what we're about. We're about understanding that child and then doing our absolute very best for them. (Manager)
A core element of work, reflecting both family practices and trauma-informed care, consisted of exploring how children were feeling through conversation and active empathic listening: ‘the most therapeutic thing we can do is just be there for those kids and listen to them’ (Staff). Identifying children’s emotions often required staff to draw on playfulness and curiosity. These ‘therapeutic’ conversations are integrated into day-to-day life and are responsive to children’s needs and cues in the moment: ‘They’re very, maybe abnormal conversations but happen during very normal routines’ (Manager).
Staff and managers reported curiosity and a trauma-informed mindset to ‘try to understand why that behaviour is coming out and what the triggers are’ (Staff), and acceptance of challenging or destructive behaviours:
I had difficulty with when I first came to Children’s House, […] a child maybe smashed up an iPad, so the next day they were getting a new one […]. But I realised that it’s because we have to let them, say that it’s okay to let those big feelings out, especially when you don’t know how to control them. (Staff)
Play, Learning, And Sensory Experiences
Managers and staff noted the importance of warmth and playfulness in the living environment, with play understood as both a family practice and trauma-informed approach; ‘Children’s House is a place where there’s generally a lot of noise. A lot of giggling.’ (Manager):
Maybe bring a bit of fun back into their lives, a bit of joy. A bit of warm care that maybe these children have not had. (Manager)
Playfulness offered opportunities for new experiences and learning. Sometimes children entering Children’s House did not know how to play and staff would teach them:
Sitting and playing with eight- or nine-year-olds in the way that you maybe would with a two- or three-year-old. […] The children will start with that parallel play to the point where actually they are able to play together. (Manager)
Sensory needs were common and trauma-sensitive approaches included relaxation techniques and physical activity, particularly outdoors, and garden play equipment. Playfulness could offer opportunities for emotional connection:
Get them running about, get them exhausted. They just seem to be able to then come home and relax. And when they’re in that relaxed state, they’re more likely to disclose to you how they’re feeling. (Staff)
Being outside was also considered helpful for children who may otherwise not have experienced ‘safe risk-taking’ (Manager); this became especially important during Covid-19 lockdowns. External organisations and professionals shared guidance with the staff on the benefits of a playful approach with the children:
We have a fantastic OT [occupational therapist]. […] It's amazing what she can divulge, you know, through the way they play. […] She would give us a lot of insight into the sort of things we need to be doing. (Staff)
Figure 1 highlights staff descriptions of how they implemented a PACE approach (Becker-Weidman and Hughes, 2008; Hughes, Golding and Hudson, 2015) to caregiving in the context of day-to-day shared living in the residential unit.

Hopeful Narratives
Managers and staff considered attitudes and culture to be central, including an underlying belief in Children’s House practices. They approached work with hope, a Barnardo’s (2022) core value:
We go into these processes believing that children are resilient, can adapt, can acquire the relationships that they need to. (Manager)
Management and language reflected values:
It’s important how we speak, and if we know that narrative is important for children, then it's just as important, the narrative that we talk about the service. (Manager)
Monthly monitoring reports were examined regarding regulatory requirements and to ensure that wording matched Children’s House values.
The assessment template was named a ‘strengths and struggles document’, considered by staff and managers to offer balanced framing, which was ‘asset-based, […] rather than looking at the deficits’ (Manager). Assessments reflected a hope-based approach regarding identifying and meeting children’s individual needs. Therapeutic needs assessments (beginning before arrival and continuing throughout children’s stay), included a sensory occupational therapy assessment, speech and language and communication assessment, and narrative work.
Staff and managers were mindful of how each child’s future may look, and sought children’s input on hobbies, pets and other preferences, ‘from day one […] probing with them, “What would you like to see in a future home?”’ (Staff). Children’s House was seen as a place where children could explore their own interests and develop a more coherent sense of identity:
They don’t really know themselves. They come with this history of, ‘Oh, he’s a real farmer’. But is that because he’s actually just had lots of placements in farms? […] It does also widen their eyes that they can make their own choices and start to figure out that they don't have to like something because their carers like it. (Manager)
Preparation For Future Placement Relationships
Prior to admission, children are assessed for attachment capability which might indicate potential later success with fostering. Assessment within Children’s House focuses on three main areas relevant to future placements and preparation for relationship transition: assessment of a child’s readiness to move on; identification of appropriate placements; and how transitions were supported by Children’s House staff.
The purpose of assessments is to place the child in the most appropriate setting for their needs, and staff are mindful of the importance of securing the best outcome for each child. A children’s strengths and struggles document and short-break experiences helped staff to clarify their needs in family or other settings, and to seek suitable carers or alternative placement types. While a long-term foster placement is often the goal, this is not always the case; four children went directly to a longer-term residential placement.
Staff described a detailed and lengthy process to identify those for whom a fostering placement was most appropriate. For those who entered residential care, this decision was reached through an equally detailed process. Managers reported the same hope for this group that their next placements would offer long-term stability and a ‘home’:
The intensity of his relationships will not work in a family setting. But we are going to be able to transition him into what will be a long, hopefully, hopefully, hopefully a long-term residential space for him and that will be his home. (Manager)
Observation of children’s progress following emotional work was a key step in determining the suitability of fostering, including improved coping mechanisms and seeing ‘value in relationships’:
A capacity for empathy and for others. And I think when we see those things, it gives us a real sense that we can hopefully support a family to care for this child. (Manager)
Observations assessed challenging behaviours to identify whether these might be ‘manageable within a family home environment as opposed to a residential environment’ (Manager), with risk assessments and support considered.
Assessments determined suitability of family life, considering children’s understanding of their narrative and willingness to engage with fostering:
They know they’re not going back to their own birth family. They know that their plan is fostering, […] until adulthood […]. They understand that and partially it’s them being on board with that. (Manager)
This was encouraged through communication with children about next steps and the temporariness of Children’s House, as a ‘journey, not a forever place’ (Manager), which helped them to anticipate and feel motivated for future placement.
Managers and staff discussed using short-break carers to allow adjustment to family life and insight into how children coped:
Can we get to the stage where they feel they're able […] to take that security with them in that sense to be able to build relationships in a family, in a family space? (Manager)
Identifying a specific foster placement involved matching a child with a family, using a ‘Matching Form’ completed by Children’s House staff, and close collaboration with the Barnardo’s Fostering Team, a field social worker and sometimes a psychologist. Staff were emphatic about their hopes that placements would last until adulthood and result in permanent relationships. Short-break carers were chosen carefully and sometimes became long-term foster carers, or often provided a source of support during later placements.
Onward transitions were supported relationally, with the ‘courtship method’ (Staff) pacing according to children’s needs. Managers described a ‘shared sense of responsibility’, while managers and staff discussed the importance of continuity of family-like relationships after leaving Children’s House:
Sending wee birthday cards and Christmas cards, just so he knows, […] I’m always thinking of him… […] he still matters to me. (Staff)
However, some children worried that staff reappearance signified disruption, and staff described being prepared to let go when this was best for a child.
Redefining ‘Success’
For some children, long-term residential or specialist hospital settings were identified as the most appropriate next placement. This also prevented exposure to further disruption from inappropriate attempts at foster placement. Consequently, the move to longer-term residential care, while not the initially hoped-for outcome upon entry to Children’s House, was recognised as beneficial and protective for children:
We need to think more about what are the outcomes because it can't just be about fostering, it has to be about care, planning for the future, and you know […] what are more realistic outcomes for a Children’s House referral and the journey. (Manager)
Furthermore, staff recognised how Children’s House practices offered some family experience at a level tolerable to the child:
Maybe a full-time [foster] placement was too big an ask after Children’s House, but some of those children had quite successful respite arrangements and we were able to give them that experience of family life in a part-time sense and that stayed with them. (Manager)
Managers reflected on the ‘success’ of Children’s House and observed a challenge surrounding negative perceptions of residential care, even if this was the most appropriate outcome for a particular child. The opportunity for staff to undertake detailed assessments and for children to receive specific therapeutic interventions through which they could reach substantial emotional and behavioural progress were seen as achievements which should be valued, even if the ultimate outcome was not what was initially desired. Managers critiqued ‘on paper’ measures of success, both regarding disrupted foster placements and residential care, contrasting these with a hopeful narrative and more individualised view of what success might look like:
We’ve given that child the ability to form relationships and feel good about himself and understand what his strengths are. But he will not look on paper like a success. […] It’s actually a failure really of our impression of residential care. Because […] in this case it is the right outcome. (Manager)
Managers reflected on what realistic outcomes might constitute success, reporting that even disrupted placements could offer the experience of stability and often relationships which could be carried into adulthood, and this in itself was ‘an achievement’ by carers and young people. When it followed a Children’s House placement, this could mean years of stability that the child was otherwise unlikely to receive, which also offered an experience of family life that children could ‘tap into in their future life’:
They've experienced something positive, stable in their life […], and they're able to pull in the reserve from that in adulthood. (Manager)
Discussion
Children’s House is a unit with a specific purpose and eligibility criteria, which recognises the challenges faced by children who have experienced multiple placement breakdowns (Strijbosch et al., 2015). It offers a period of stability to develop emotional capacity and relational skills to enable children to enter a long-term foster placement, or other stable alternative, until adulthood. The intention is that children will have the lasting supportive relationships with caring adults, which research indicates may offer increased social capital, encouragement and resilience, particularly at key transitions (Blakeslee and Best, 2019).
Emphasis is placed on emotional co-regulation and demonstrating to children that carers are capable of meeting their needs. Providing a family-like environment, sense of normality, and stability are prioritised in the day-to-day life of Children’s House. Consistent with social constructions of family (Kendrick, 2013; Fowler, 2016; Gwenzi, 2020), everyday routines represent family-like practices, supporting relationship-building and ‘notions of relatedness’ (Kendrick, 2013: 79). An explicitly loving ethos and demonstrably affectionate relationships appear to have liberated staff from some anxieties reported by professionals in other residential contexts (Brown, Winter and Carr, 2018). While safety and robust safeguarding procedures are crucial, staff and managers also discussed the value that emotional intimacy brings to relationships with children. Reflectively engaging with these challenges presents an alternative to more detached professional approaches. While children’s safety is paramount, risk-aversion is unhelpful if staff feel afraid to engage in meaningful relationship-building.
Acknowledging the impacts of children’s experiences on their relationships (Samuels and Pryce, 2008; Blakeslee and Best, 2019; Okpych and Gray, 2021; Tahkola et al., 2021) informs working practices and trauma-awareness shapes routines. Working at Children’s House requires staff to connect emotionally with children and provide affectionate care, necessitating boundaries and self-reflection. This approach does not suit everyone but resonates with many staff, who find it rewarding.
All work in Children’s House has a trauma-informed basis, but there is a focus on identifying and meeting individual needs, including via specialist input. Relationship work considers complex attachment histories (Bowlby 1988; Burbidge, Keenan and Parry, 2020; Tahkola et al., 2021) and helps children learn to love and trust, while narrative work (Coman et al., 2016; McGill et al., 2018), helps them to understand their history and identity. Day-to-day, trauma-awareness infuses all relational interactions, with caregiving informed by the PACE approach (Becker-Weidman and Hughes, 2008; Hughes, Golding and Hudson, 2015) to understand how children are feeling and build their self-worth, coping strategies and behaviours. Through play, exploration and sensory experiences that are appropriate to their needs, children develop skills and self-confidence while having fun.
Children’s House facilitates an in-depth and detailed assessment of each child’s coping mechanisms, behavioural difficulties, sense of value in relationships, and their capacity and willingness to engage with foster family relationships. Use of short-break carers provides insight into children’s coping within a family home. Adjusting the pace and timing of transitions and having continuity of connection with key adults who share important information supports children’s individual journeys from short-term to long-term placement (Nicol, 2016). Residential and family placement staff collaborate closely in matching and moves. Transitions are paced according to children’s needs, Children’s House provides a background presence and support, and continuing relationships with Children’s House staff are encouraged.
Of the 29 residents of Children’s House who are now aged over 18 years, over half (n = 16) remained in family placements until adulthood. Two experienced relational permanence (McSherry and Fargas Malet, 2018) despite placement disruption in later adolescence, demonstrating that young people and their foster family can sustain mutually valued connections despite relational challenges and early instability (MacDonald and Marshall, 2021). However, the challenges of achieving stability are significant (James et al., 2004; Rubin et al., 2004; Hussey and Guo, 2005), and some placements do disrupt with children returning to residential care. For these children who experienced further disruption, their time in Children’s House (25 months on average) offers stability, albeit time-limited, with safe, warm family-like care.
Some children moved from Children’s House to other residential settings. Staff and managers discussed the challenges of measuring success when residential care is often perceived as a last resort. Close relationships in Children’s House allow for detailed understanding and robust assessment of children’s needs to identify the best placement option for individual children. For some, a stable onward placement in residential care avoided the negative impact of further placement breakdown, as might have been the inevitable outcome of a move to foster care. Consequently, staff and managers described moves to residential settings positively as an achievement for the particular child. Further research might explore how individualised measures of success can more sensitively identify positive outcomes for each child.
Importantly, relationships with staff and foster carers which Children’s House supports may help to provide an emotional and practical support network, which research indicates may assist to alleviate some of the challenges faced by children who experience multiple disruption (Samuels and Pryce, 2008; Blakeslee and Best, 2019; Okpych and Gray, 2021), as well as aiding to develop resilience. Children’s House provides family-like practices appropriate to a specific age group. Given that establishing supportive relationships is crucial throughout children’s lives, further research might seek to examine how trauma-informed family-like relationships might be established with different age groups.
Conclusion
Repeated placement breakdowns are detrimental to children’s wellbeing, and this harm accumulates with subsequent moves. Enabling all young people in alternative care to benefit from lasting supportive relationships is, and should remain, a policy and practice priority (Boddy, 2013). This service evaluation of Children’s House gives cause for optimism that a cycle of instability can be interrupted, even when children have experienced multiple foster placement disruption, and warrants further study, which should in turn prioritise children’s voices and lived subjective realities. This service evaluation elicited the views of staff and managers but not those of the young people themselves. However, children and young people should be central to building research evidence, and the opportunity to have their views and experiences appropriately listened and responded to is essential for protecting their rights and interests (Gilligan, 2014). We also do not know from this evaluation the quality of their lived experience after leaving Children’s House. Ongoing research is needed to more fully understand the calibre of staff–child relationships in residential care and their impact on children’s capacity to avail themselves of nurturing relationships and social support longer-term and outside of this setting (Hart, LaValle and Holmes, 2015).
Notwithstanding its limitations, this paper has described how family-like relationships in the trauma-informed caregiving environment of Children’s House prepare children for long-term onward placements. While the primary aspiration was for children to ultimately benefit from stable foster placements, assessment practices and staff definitions of ‘success’ were highly individualised. This challenges the predominant view of residential care as the placement of last resort, in that it may be preferable to family placement for some children, but also highlights the importance of robust assessment, and getting to know children well, to identify which individual young people will benefit from a family placement and at what point in their care journey (Hart, LaValle and Holmes, 2015).
While not all children avoided further disruption, many experienced stable family placements and/or relational continuity into adulthood. Family-like caregiving routines were important preparation for future family life. Relationships were built on genuine emotional connection, using trauma-informed approaches such as PACE, to enable co-regulation and trust. This approach requires an explicit commitment at all organisational levels, close collaboration between teams, staff training and ongoing support, and continual critical reflection, both internally and through external oversight. Organisations seeking to undertake this approach must empower staff to safely engage in close relationships with children, but realistically so, supported emotionally and equipped with appropriate knowledge and trauma awareness.
Complexe Systémique: key points
The study has the merit of taking seriously an option often seen as second-best. Children’s House does not see itself as the opposite of family, but as a place of passage that borrows family gestures: letters before arrival, shared meals, a goodnight hug, cards sent after leaving. Systemic clinicians will recognise familiar landmarks: the child is no longer held responsible for the breakdowns, professional records stop placing that burden on them, and success is redefined case by case, including when the outcome is another residential home. The service also links two teams, residential and fostering, and paces transitions gradually: this is work on the placement system as much as on the child. The limits are clear: a service evaluation requested by the provider, the voice of staff alone, without that of children or foster carers, and trajectories described without a comparison group. Read alongside the article on protective factors against foster placement breakdown, and the article on non-violent resistance in a residential care home.
Notes from the original
Note: Ages are approximate (within 3–6 months); ‘Residential placement’ includes residential unit (n = 9), specialist residential unit (n = 3), boarding school (n = 1) and hospital (n = 1).
References
Ainsworth F, Hansen P (2015) Therapeutic residential care: Different population, different purpose, different costs. Children Australia 40(4): 342–347.
Ainsworth MDS, Blehar MC, Waters E, Wall SN (1978) Patterns of Attachment: A Psychological Study of the Strange Situation. Hillsdale, NJ: Erlbaum.
Barnardo’s (2022) Our Values. Available at: www.barnardos.org.uk/our-basis-and-values
Becker-Weidman A (2006) Treatment for children with trauma-attachment disorders: Dyadic Developmental Psychotherapy. Child and Adolescent Social Work Journal 23(2): 147–171.
Becker-Weidman A, Hughes D (2008) Dyadic Developmental Psychotherapy: An evidence-based treatment for children with complex trauma and disorders of attachment. Child & Family Social Work 13(3): 329–337.
Blakeslee JE, Best JI (2019) Understanding support network capacity during the transition from foster care: Youth-identified barriers, facilitators, and enhancement strategies. Children and Youth Services Review 96: 220–230. doi.org/10.1016/j.childyouth.2018.11.049
Boddy J (2013) Understanding permanence for looked after children: A review of research for the Care Inquiry. Available at: thecareinquiry.files.wordpress.com/2013/04/understanding-permanence-for-lac.pdf
Bowlby J (1988) A Secure Base: Clinical Applications of Attachment Theory. London: Routledge.
Braun V, Clarke V (2006) Using thematic analysis in psychology. Qualitative Research in Psychology 3(2): 77–101.
Brown T, Winter K, Carr N (2018) Residential child care workers and relationship based practice in a culture of fear. Child & Family Social Work 23(4): 657–665. doi.org/10.1111/cfs.12461
Burbidge CE, Keenan J, Parry S (2020) ‘I’ve made that little bit of difference to this child’: Therapeutic parents’ experiences of trials and triumphs in therapeutic children’s homes. Journal of Workplace Behavioral Health 35:4: 256–278.
Coman W, Dickson S, McGill L, Rainey M (2016) Why am I in care? A model for communicating with children about entry to care that promotes psychological safety and adjustment. Adoption & Fostering 40(1): 49–59.
Dozier M, Kaufman J, Kobak R, O’Connor TG, Sagi-Schwartz A, Scott S, Shauffer C, Smetana J, van IJzendoorn MH, Zeanah CH (2014) Consensus statement on group care for children and adolescents: A statement of policy of the American Orthopsychiatric Association. American Journal of Orthopsychiatry 84(3): 219–225. doi.org/10.1037/ort0000005
Fowler N (2016) ‘We’re like one, big, dysfunctional family’: Struggling to define the role of residential child care workers. Institutionalised Children Explorations and Beyond 3(1): 77–90. doi.org/10.5958/2349-3011.2016.00007.4
Garcia Quiroga M, Hamilton-Giachritsis C (2017) Getting involved: A thematic analysis of caregivers’ perspectives in Chilean residential children’s homes. Journal of Social and Personal Relationships 34(3): 356–375.
Gilligan R (2014) Foreword. In: Whittaker JK, del Valle JF, Holmes L (eds) Therapeutic Residential Care for Children and Youth: Developing Evidence-Based International Practice. London: Jessica Kingsley Publishers.
Gwenzi GD (2020) Constructing the meaning of ‘Family’ in the context of out-of-home care: An exploratory study on residential care leavers in Harare, Zimbabwe. Emerging Adulthood 8(1): 54–63. doi.org/10.1177/2167696818800846
Gypen L, Vanderfaeillie J, De Maeyer S, Belenger L, van Holen F (2017) Outcomes of children who grew up in foster care: Systematic review. Children and Youth Services Review 76: 74–83. doi.org/10.1016/j.childyouth.2017.02.035
Hart D, La Valle I, Holmes L (2015) The Place of Residential Care in the English Child Welfare System. London: Department for Education. Available at: assets.publishing.service.gov.uk/government/uploads/system/uploads/attachment_data/file/435694/Residential_care_in_the_English_child_welfare_system.pdf
Havlicek JR, Garcia AR, Smith DC (2013) Mental health and substance use disorders among foster youth transitioning to adulthood: Past research and future directions. Children and Youth Services Review 35: 194–203.
Huefner J, Ainsworth F (2021) Commentary: Recognizing the value of the milieu in therapeutic residential care for children and youth. Residential Treatment for Children & Youth 38(3): 324–335. doi/org/10.1080/0886571X.2021.1915225
Hughes D, Golding K, Hudson J (2015) Dyadic Developmental Psychotherapy (DDP): The development of the theory, practice and research base. Adoption & Fostering 39(4): 356–365. doi/org/10.1177/0308575915610943
Hussey DL, Guo S (2005) Characteristics and trajectories of treatment foster care youth. Child Welfare 84(4): 485–506.
Jakobsen TB (2013) Anti-social youth? Disruptions in care and the role of ‘behavioral problems’. Children and Youth Services Review 35(9): 1455–1462. doi.org/10.1016/j.childyouth.2013.05.012
James S, Landsverk J, Slymen DJ, Leslie LK (2004) Predictors of outpatient mental health service use: The role of foster care placement change. Mental Health Services Research 6: 127–141. doi.org/10.1023/B:MHSR.0000036487.39001.51
Johnson D (2017) A Best Fit Model of Trauma-informed Care for Young People in Residential and Secure Services: Report. Scotland: Kibble Education and Care Centre. Available at: www.kibble.org/wp-content/uploads/2017/08/best-fit-model-trauma-informed-care.pdf
Kendrick A (2013) Relations, relationships and relatedness: Residential child care and the family metaphor. Child & Family Social Work 18(1): 77–86.
Lone A, Paulsen E (2018) Is it love? A study of young people's personal impressions and experiences of relationships in residential care in a Norwegian treatment collective. Scottish Journal of Residential Child Care 17(2). doi.org/10.17868/strath.00084645
MacDonald M, Marshall G (2021) Lasting Relationships in Foster Care: Research for Practice Summary. Belfast: Barnardo’s. Available at: pureadmin.qub.ac.uk/ws/portalfiles/portal/302609718/23002_Lasting_Relationships_in_Foster_Care_Summary_Single_page.pdf
McGill L, Coman W, McWhirter J, O’Sullivan C (2018) Social workers’ experiences of using the narrative model to talk to children about why they are in care and other sensitive issues. Adoption & Fostering 42(1): 49–57.
McIntosh I, Dorrer N, Punch S, Emond R (2011) ‘I know we can’t be a family, but as close as you can get’: Displaying families within an institutional context. In: Dermott E, Seymour J (eds) Displaying Families: A New Concept for the Sociology of Family Life. Basingstoke: Palgrave Macmillan, pp.175–194.
McSherry D, Fargas Malet M (2018) The extent of stability and relational permanence achieved for young children in care in Northern Ireland. Children Australia 43(2): 124. doi.org/10.1017/cha.2018.18
Neimetz C (2011) Navigating family roles within an institutional framework: An exploratory study in one private Chinese orphanage. Journal of Child and Family Studies 20(5): 585–595.
Nicol A (2016) From residential unit to permanent foster care: Reflections on one child’s journey towards legal permanence in Scotland. Scottish Journal of Residential Child Care 15(1). Available at: strathprints.strath.ac.uk/84800/1/Nicol_etal_SJRCC_2016_From_residential_unit_to_permanent_foster_care.pdf
Oosterman M, Schuengel C, Wim Slot N, Bullens RAR, Doreleijers TAH (2007) Disruptions in foster care: A review and meta-analysis. Children and Youth Services Review 29(1): 53–76. doi.org/10.1016/j.childyouth.2006.07.003
Okpych NJ, Gray LA (2021) Ties that bond and bridge: Exploring social capital among college students with foster care histories using a novel social network instrument (FC-Connects). Innovative Higher Education 46(6): 683–705. doi.org/10.1007/s10755-021-09553-x
Punch S, McIntosh I, Emond R, Dorrer N (2009) Food and relationships: Children’s experiences in residential care. In: James A, Kjørholt AT, Tingstad V (eds) Children, Food and Identity in Everyday Life. Basingstoke: Palgrave Macmillan, pp. 149–171.
Rubin DM, Alessandrini EA, Feudtner C, Mandell DS, Localio AR, Hadley TP (2004) Placement stability and mental health costs for children in foster care. Pediatrics 113(5): 1336–1341.
Samuels GM, Pryce JM (2008) ‘What doesn't kill you makes you stronger’: Survivalist self-reliance as resilience and risk among young adults aging out of foster care. Children and Youth Services Review 30(10): 1198–1210. doi.org/10.1016/j.childyouth.2008.03.005
Schofield G, Beek M (2018) Attachment Handbook for Foster Care and Adoption (2nd edn.). London: CoramBAAF.
Smart M, Thorpe A (2020) From ‘Another kind of home’ to ‘A different kind of family’: Re-understanding how residential child care can work. Scottish Journal of Residential Child Care 19(1). Available at: core.ac.uk/reader/554437870
Strijbosch ELL, Huijs JAM, Stams GJJM, Wissink IB, van der Helm GHP, De Swart JJW, van der Veen Z (2015) The outcome of institutional youth care compared to non-institutional youth care for children of primary school age and early adolescence: A multi-level meta-analysis. Children and Youth Services Review 58: 208–218.
Tahkola EM, Metsäpelto RL, Ruohotie-Lyhty M, Poikkeus AM (2021) Relationships of young adults with foster care backgrounds: Tensions and management strategies. Child & Family Social Work 26(3): 358–369. doi.org/10.1111/cfs.12816
Trask B (2009) Globalization and Families: Accelerated Systemic Social Change. New York, NY: Springer Science & Business Media.
United Nations (1989) United Nations Convention on the Rights of the Child. Geneva: United Nations.
Weisz JR, Kuppens S, Eckshtain D, Ugueto AM, Hawley KM, Jensen-Doss A (2013) Performance of evidence-based youth psychotherapies compared with usual clinical care: A multilevel meta-analysis. JAMA Psychiatry 70(7): 750–761.
Welch V (2018) Talking back to ‘family’, ‘family troubles’ and ‘the looked-after child’. Sociological Research Online 23: 197–218.
What Works Centre for Children’s Social Care (2019) Summary: Residential Care. Available at: whatworks-csc.org.uk/evidence/evidence-store/intervention/residential-care/
Wingfield M, Gurney-Smith B (2019) Adoptive parents’ experiences of dyadic developmental psychotherapy. Clinical Child Psychology and Psychiatry 24(4): 661–667.
Reformatted republication of Interrupting a cycle of placement instability with short-term residential care: Trauma-informed family-like relational practice in one specialist unit, by Mandi MacDonald and Kathryn Gillespie, Adoption & Fostering, vol. 47, no 4, p. 379-399 (2023), doi: 10.1177/03085759231212499, under a CC BY 4.0 licence. Edition and layout: Complexe Systémique, September 2026 — the work has been modified under the terms of the licence (table note grouped in the notes). Neither the authors nor the publisher are responsible for this edition; the original version prevails.
This is the original article “Interrupting a cycle of placement instability with short-term residential care: Trauma-informed family-like relational practice in one specialist unit”, published in Adoption & Fostering (2023) under a CC BY 4.0 licence. Republished by Complexe Systémique: the author’s text is unchanged; only the presentation has been adapted for reading online, as set out at the head of this page.
Read the original articleHow to cite this article
MacDonald, M., et Gillespie, K. (2023). Interrupting a cycle of placement instability with short-term residential care: Trauma-informed family-like relational practice in one specialist unit. Complexe Systémique. https://app.complexe-systemique.com/en_GB/articles/interrupting-a-cycle-of-placement-instability-with-short-term-residential-care-trauma (Original work published in 2023 in Adoption & Fostering, 47(4), 379-399 (2023); republished in 2023 by Adoption & Fostering, https://journals.sagepub.com/doi/10.1177/03085759231212499)
To go further
- Le cadre restauratif : une théorie ancrée des facteurs de protection contre les ruptures de placement en famille d’accueilAgainst placement breakdown.
- La résistance non violente en foyer pour jeunes aux comportements à haut risque : l’expérience des équipesNon-violent resistance in residential care.
- Être parent, sans l’être : une théorie ancrée de l’accueil en milieu familialBeing a parent, but not.
Related articles
 Scientific
Family group conference provision across the lifespan of child welfare intervention: A mixed-method realist-informed evaluation comparing three stages of welfare concern
Early help, child protection or children in care: among 155 UK families, experiences and outcomes of family group conferences vary very little by stage.
 Scientific
How can we BeST? meet the needs of adoptive families? Relevant findings from a major Randomised Controlled Trial of infants in foster care in the UK
The BeST? trial (488 infants in care in the UK) reread for adoption: holistic, ongoing assessment of children and a move to dual registration.
 Scientific
The Role of Parental Expressed Emotion and Loss-Specific Parental Responses in Children’s Loss-Related Outcomes Following Traumatic Loss: A Mixed-Methods Observational Study
After a road-traffic bereavement, parental criticism goes with the child's depression, positive appraisals of the loss with better well-being.
 Scientific
Implementing Family Group Decision-Making within statutory child protection social work in Scotland: Challenges and opportunities
Family group decision-making offered automatically in Scottish child protection: families find a voice, social workers doubt the plans, and everyone wants it offered earlier.